TAVNEOS remains available. For questions about the recent updates on TAVNEOS® and what this means for you, please review Amgen's Statement
This link is updated regularly to keep the community informed on the latest information.
ORIGINAL ADVOCATE ADJUDICATION FROM 2019
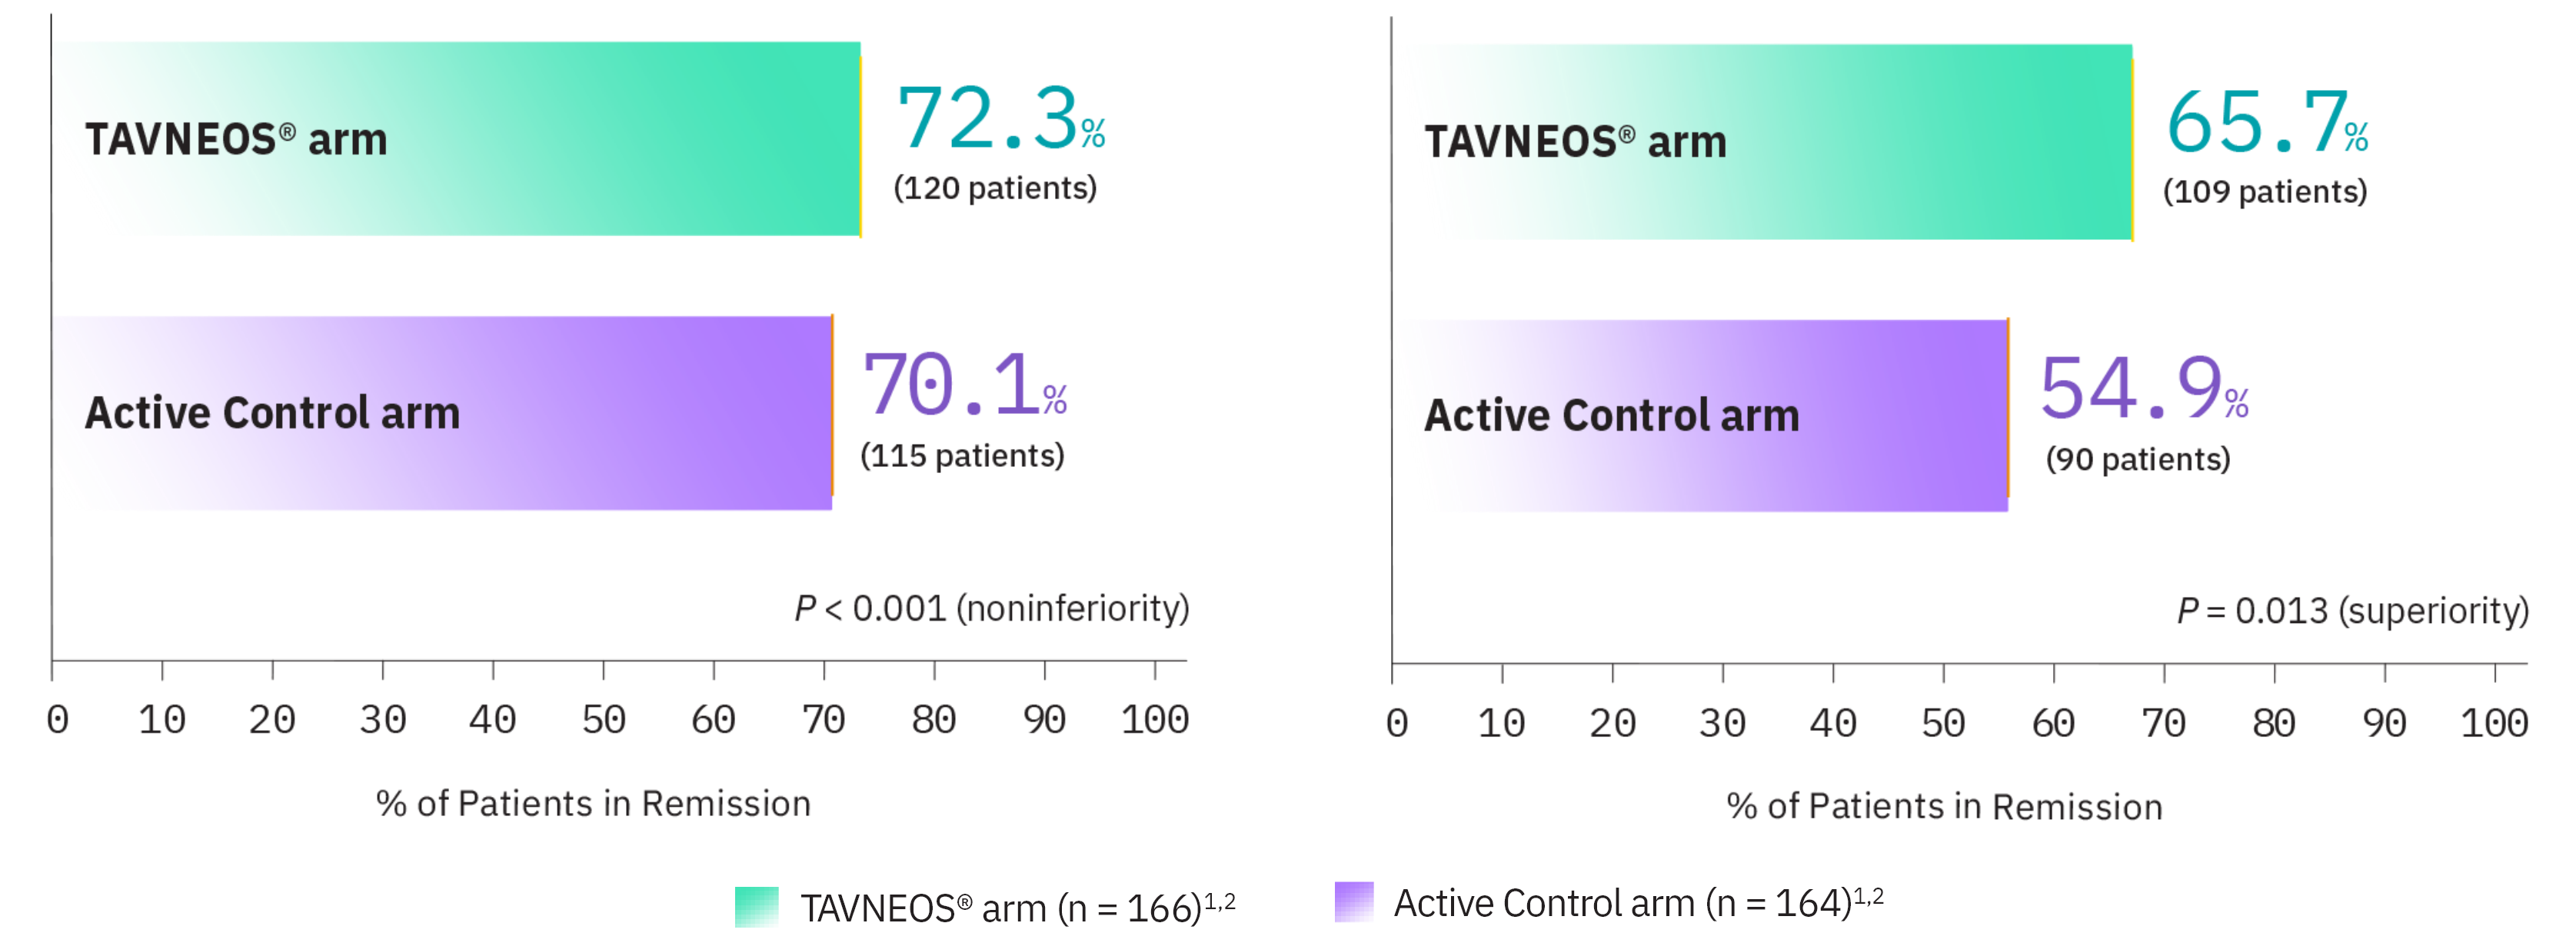
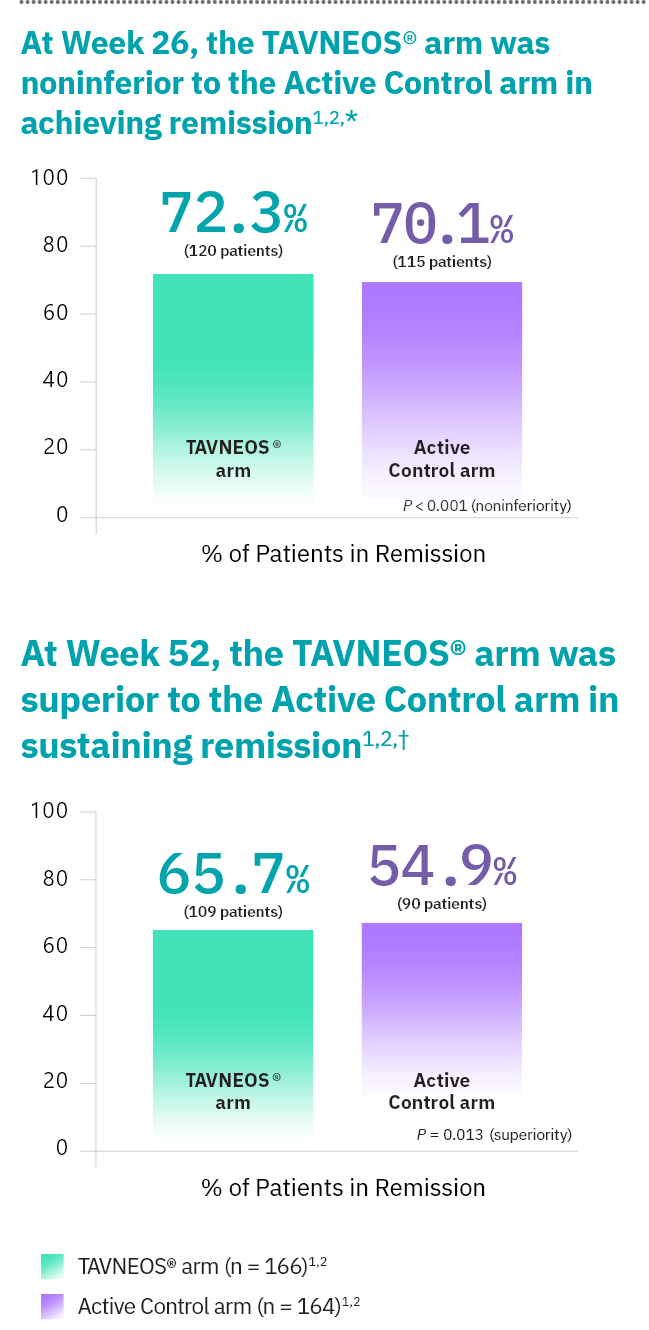
The TAVNEOS® arm was superior compared to the Active Control arm in sustaining remission at 1 year1,2
At Week 26, the TAVNEOS® arm was noninferior to the Active Control arm in achieving remission1,2,*
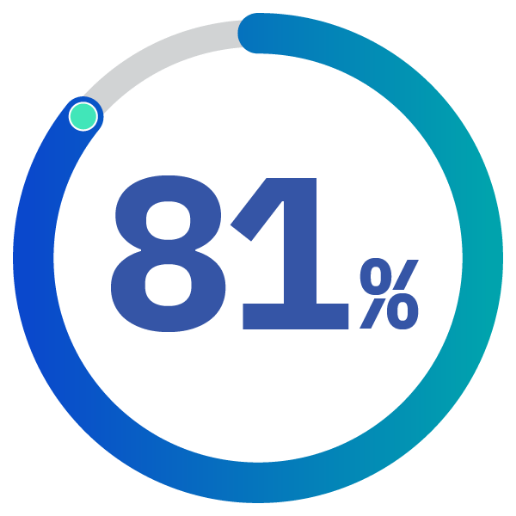
At Week 52, the TAVNEOS® arm was superior to the Active Control arm in sustaining remission1,2,†
INDEPENDENT ADVOCATE RE-ADJUDICATION FROM 2026
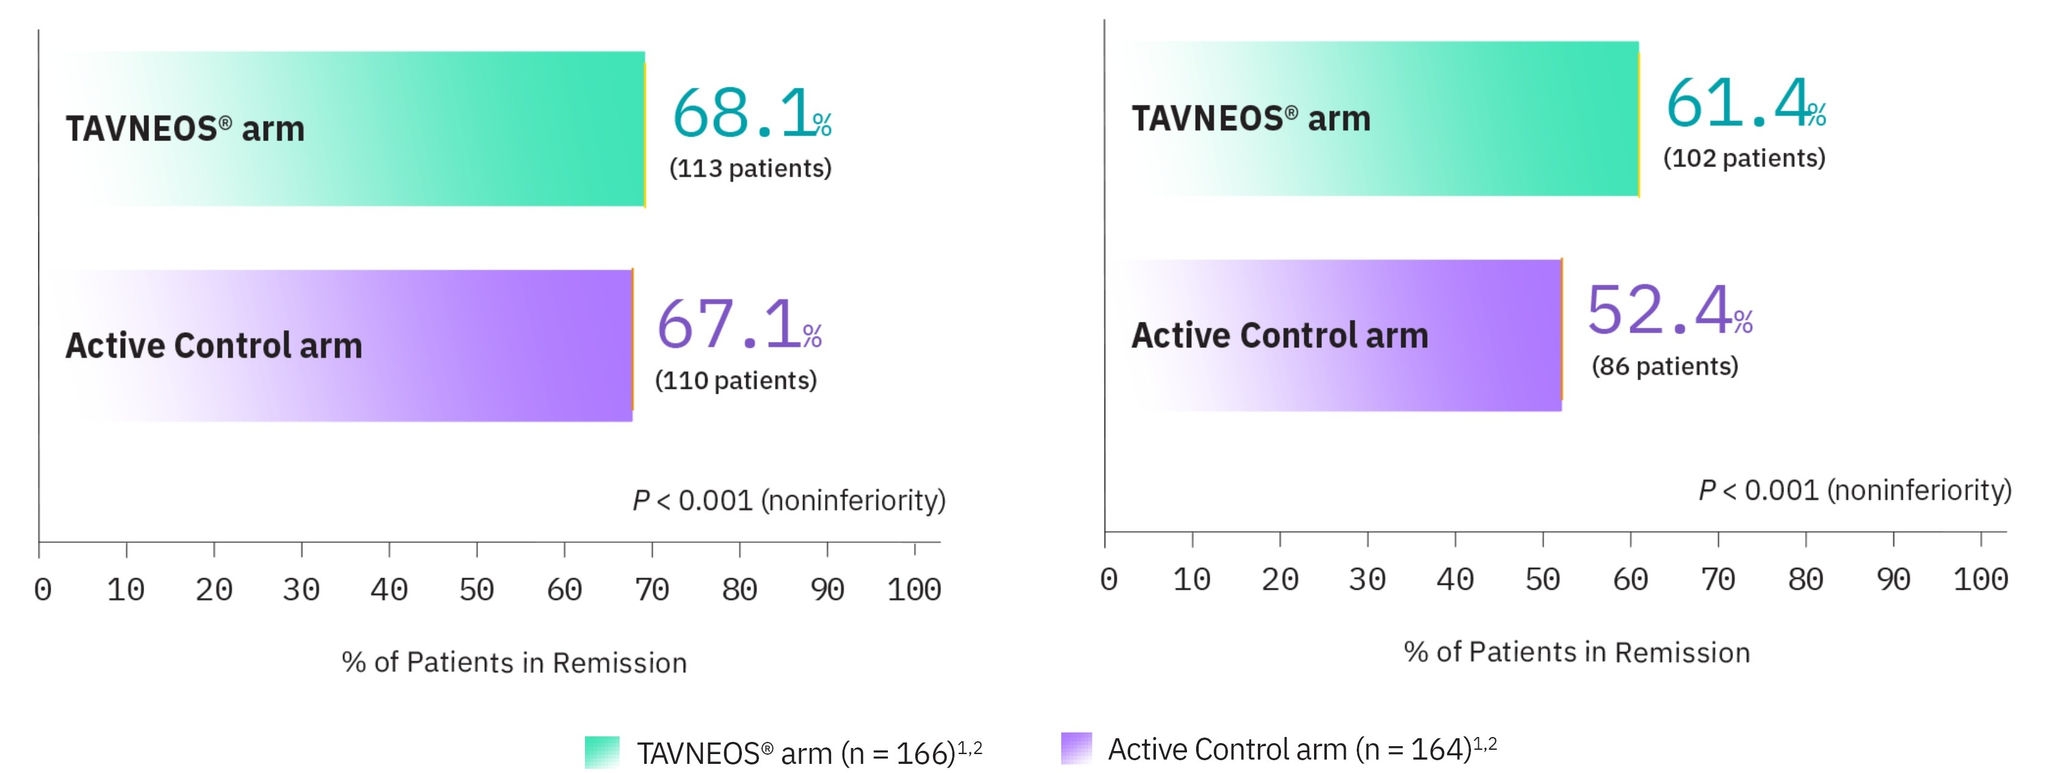
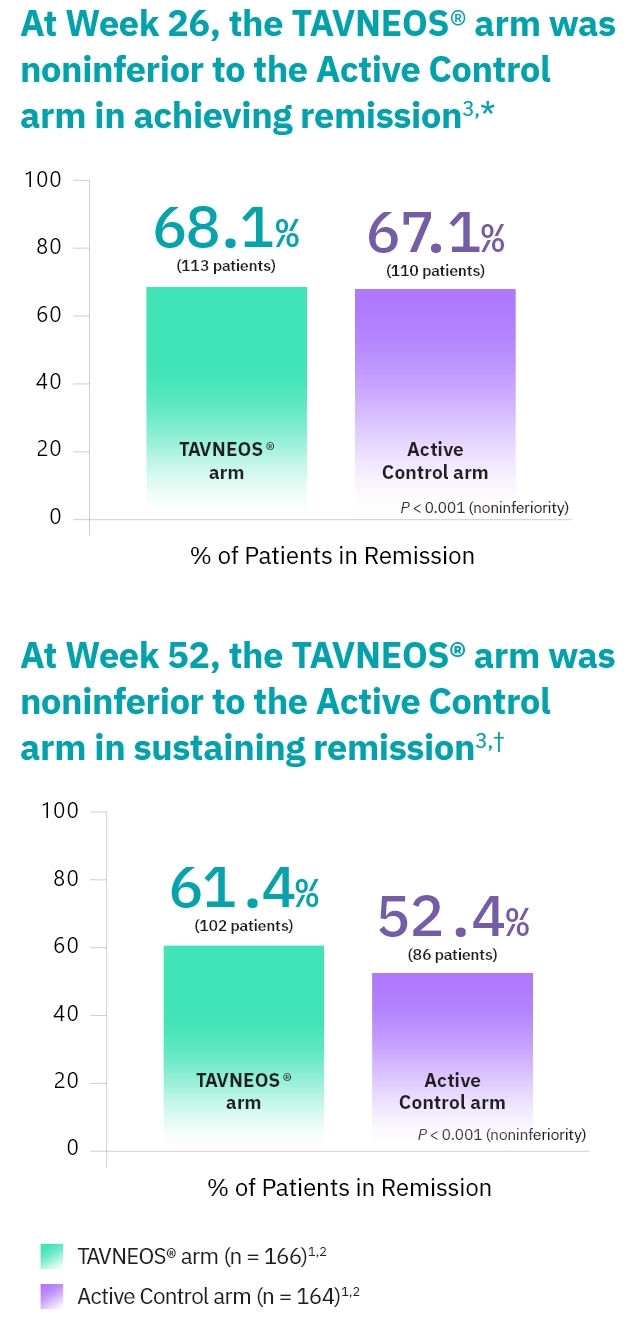
An independent, blinded re-adjudication reported high rates of remission and sustained remission with TAVNEOS® 3,4
The retrospective re-adjudication of the ADVOCATE primary endpoints was performed by a newly selected and trained adjudication committee using the original data packages without modification, and no access to prior patient-level adjudication decisions. No other outcomes were assessed.4
At Week 26, the TAVNEOS® arm was noninferior to the Active Control arm in achieving remission3,*
At Week 52, the TAVNEOS® arm was noninferior to the Active Control arm in sustaining remission3,†
Patients in the TAVNEOS® arm experienced a reduction in mean glucocorticoid exposure by approximately 2.2 g6,*
Total Prednisone-Equivalent Dose (Oral or IV)6
| TAVNEOS® arm (n = 166) | Active Control arm (n = 164) | |
|---|---|---|
| Median dose | 600 mg | 3097.5 mg |
| Mean dose | 1675.5 mg | 3846.9 |
Glucocorticoids were allowed in both treatment arms as:1
- Pre-medication for rituximab to reduce hypersensitivity reactions
- Taper after glucocorticoids given during the screening period
- Treatment of persistent vasculitis, worsening of vasculitis, or relapses
- Non-vasculitis reasons, such as adrenal insufficiency
The incidence of non-study-supplied glucocorticoid exposure was balanced between both arms. Results are descriptive.7
*Prednisone equivalent dose per patient.
CYC = cyclophosphamide; EULAR = European Alliance of Associations for Rheumatology; RTX = rituximab.
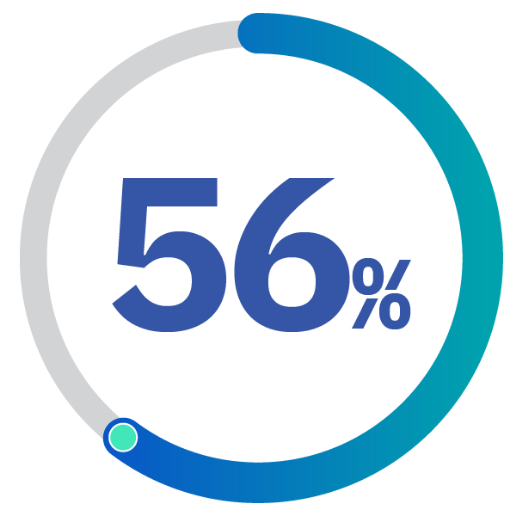
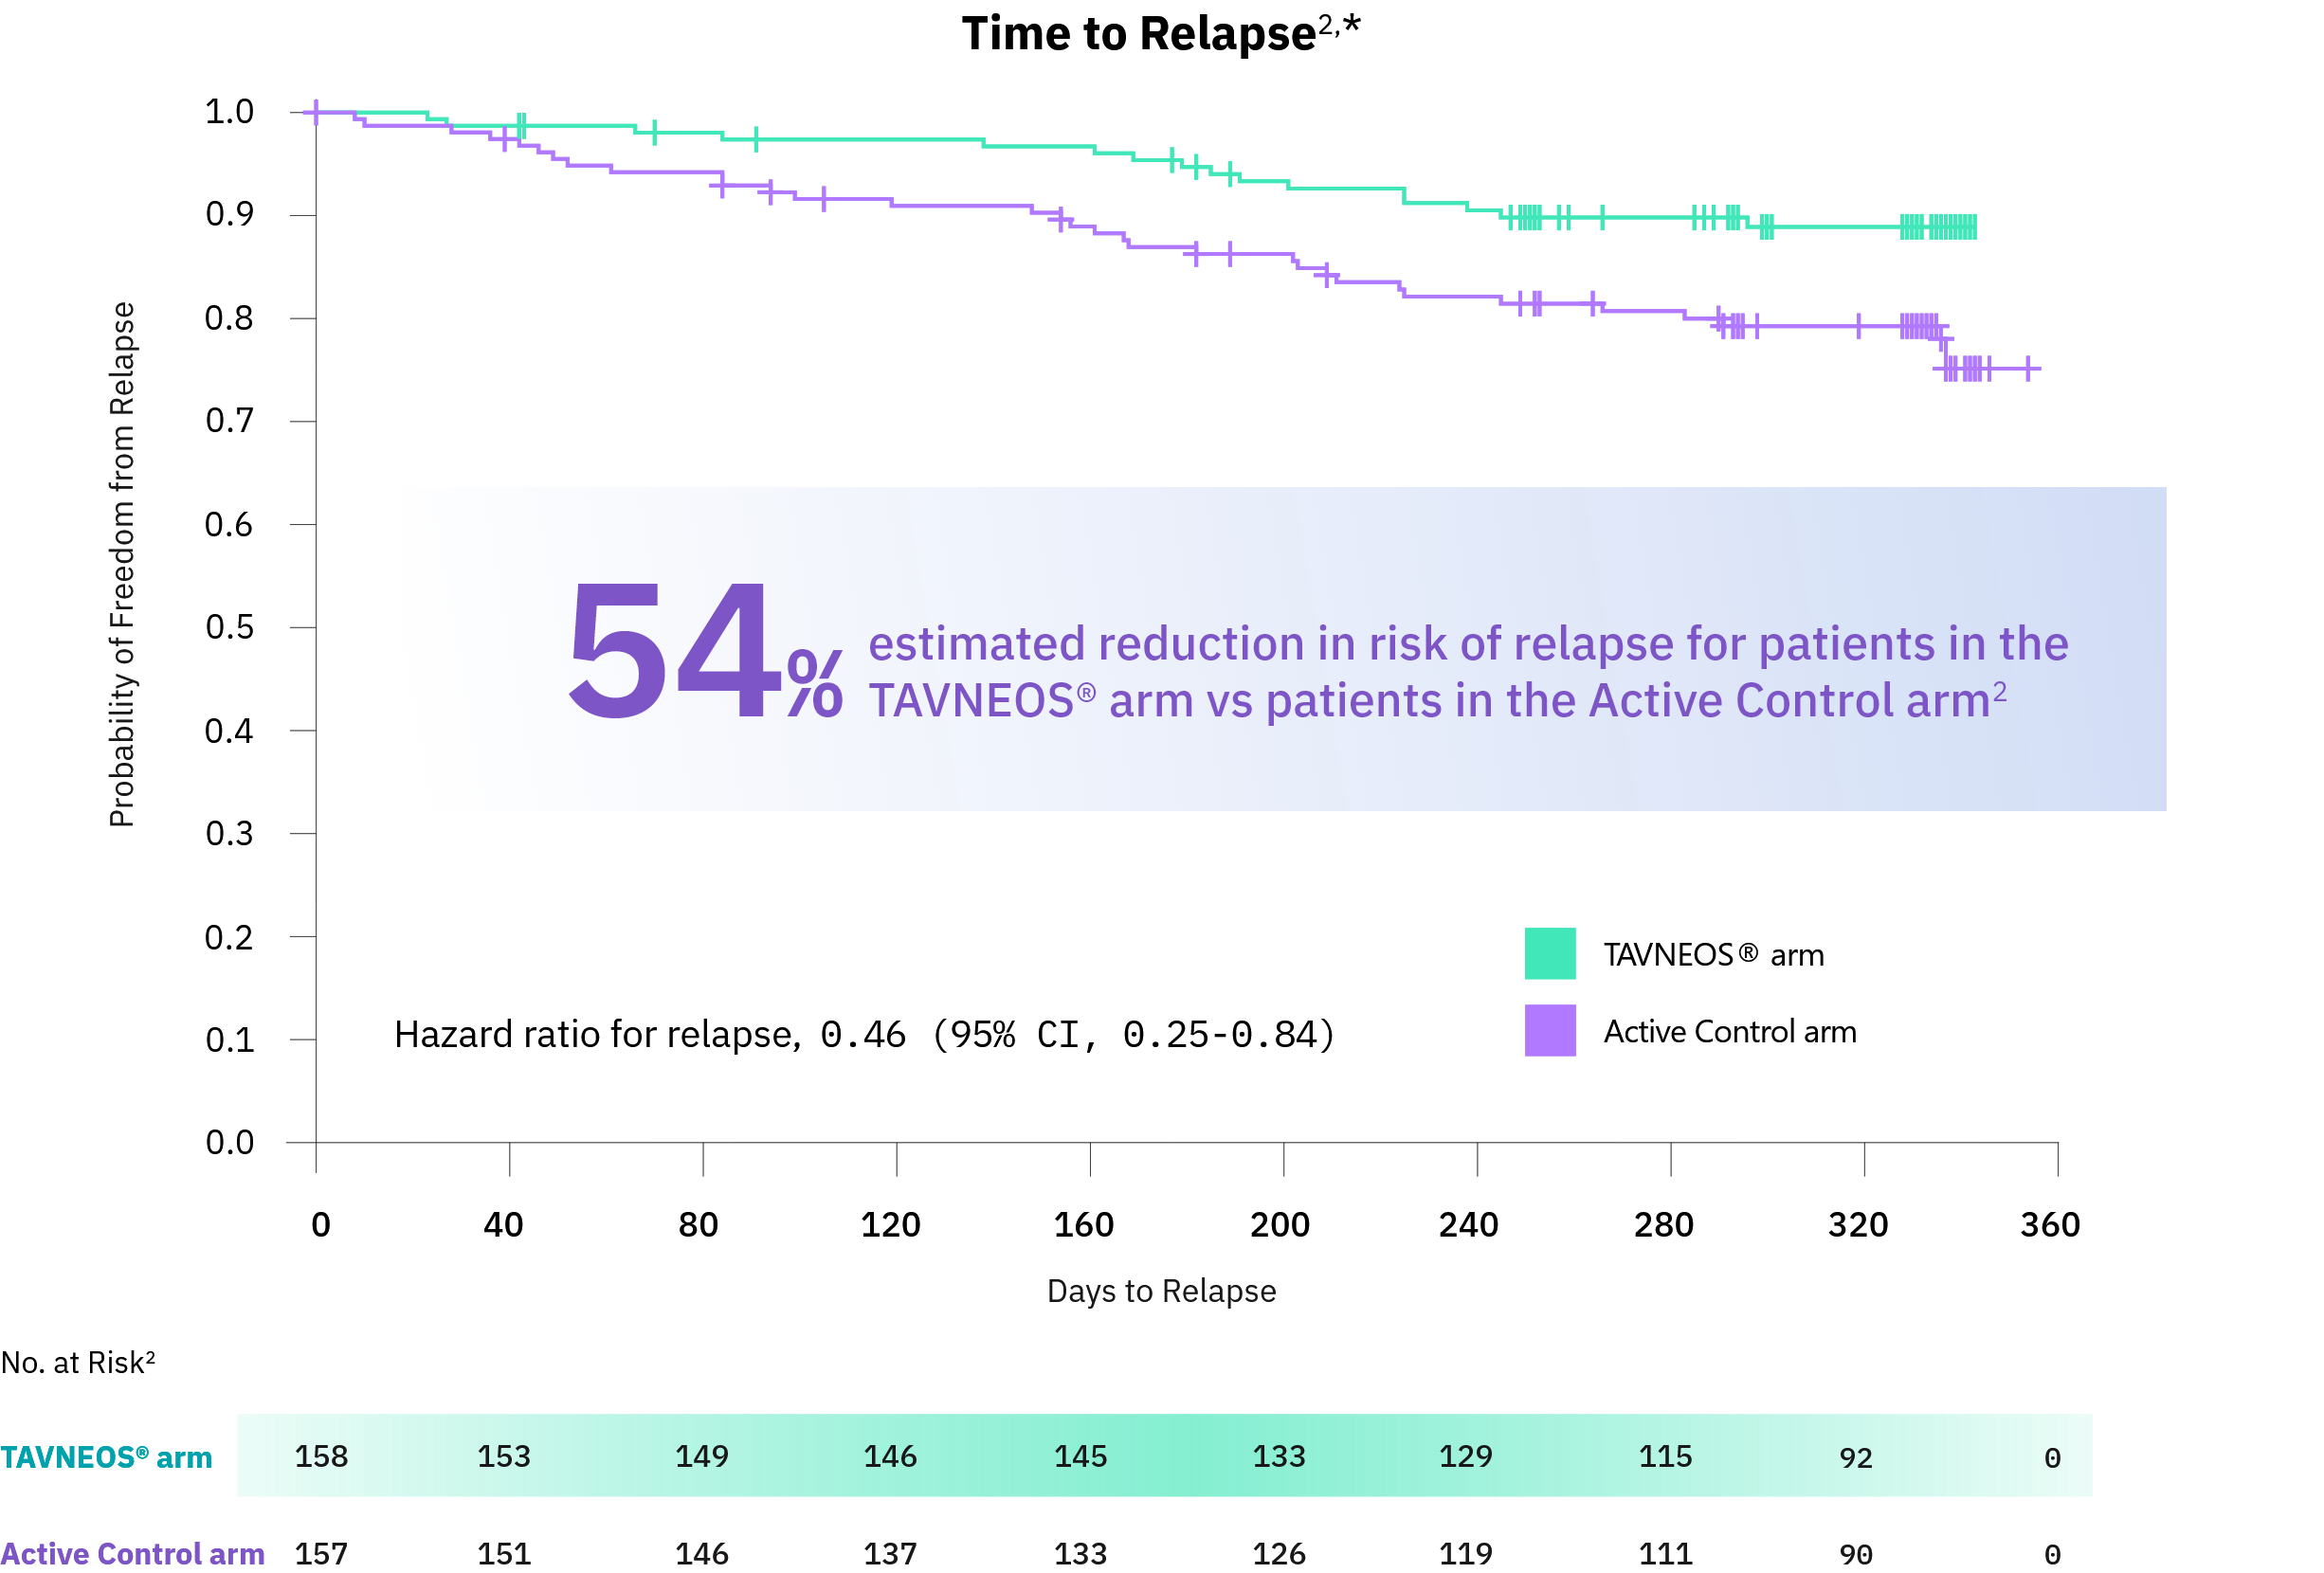
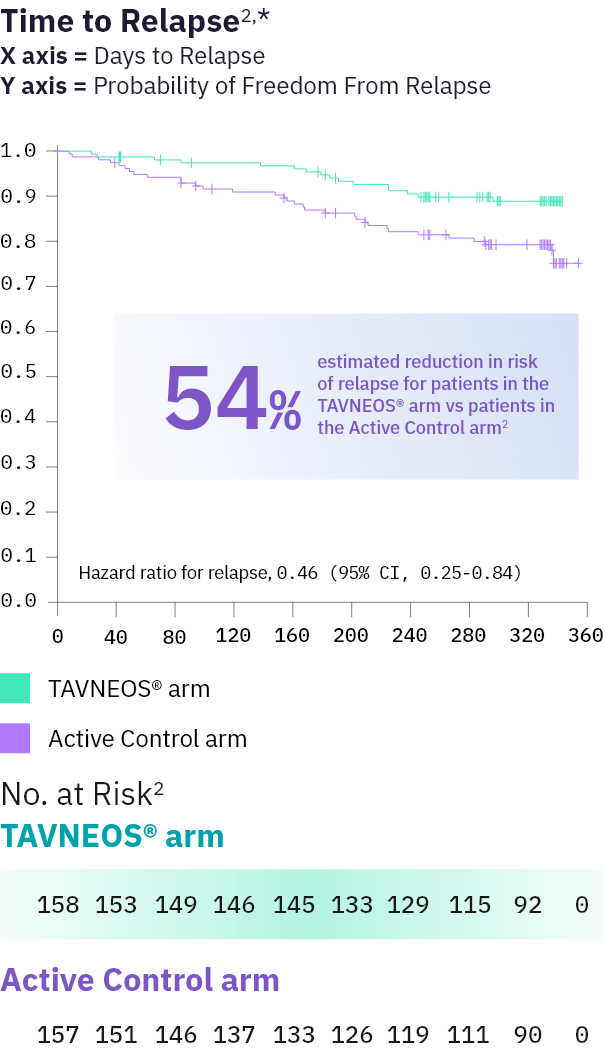
The TAVNEOS® arm saw a reduced risk of relapse by half compared to the Active Control arm2
10.1% of patients in the TAVNEOS® arm experienced a relapse, compared with 21% of patients in the Active Control arm2
Prespecified secondary endpoint not adjusted for multiplicity and subject to post-randomization variable dependence. Results should be interpreted with caution.2
*Adapted from Jayne DRW, et al. N Engl J Med. 2021;384:599-609.
BVAS = Birmingham Vasculitis Activity Score; CI = confidence interval.
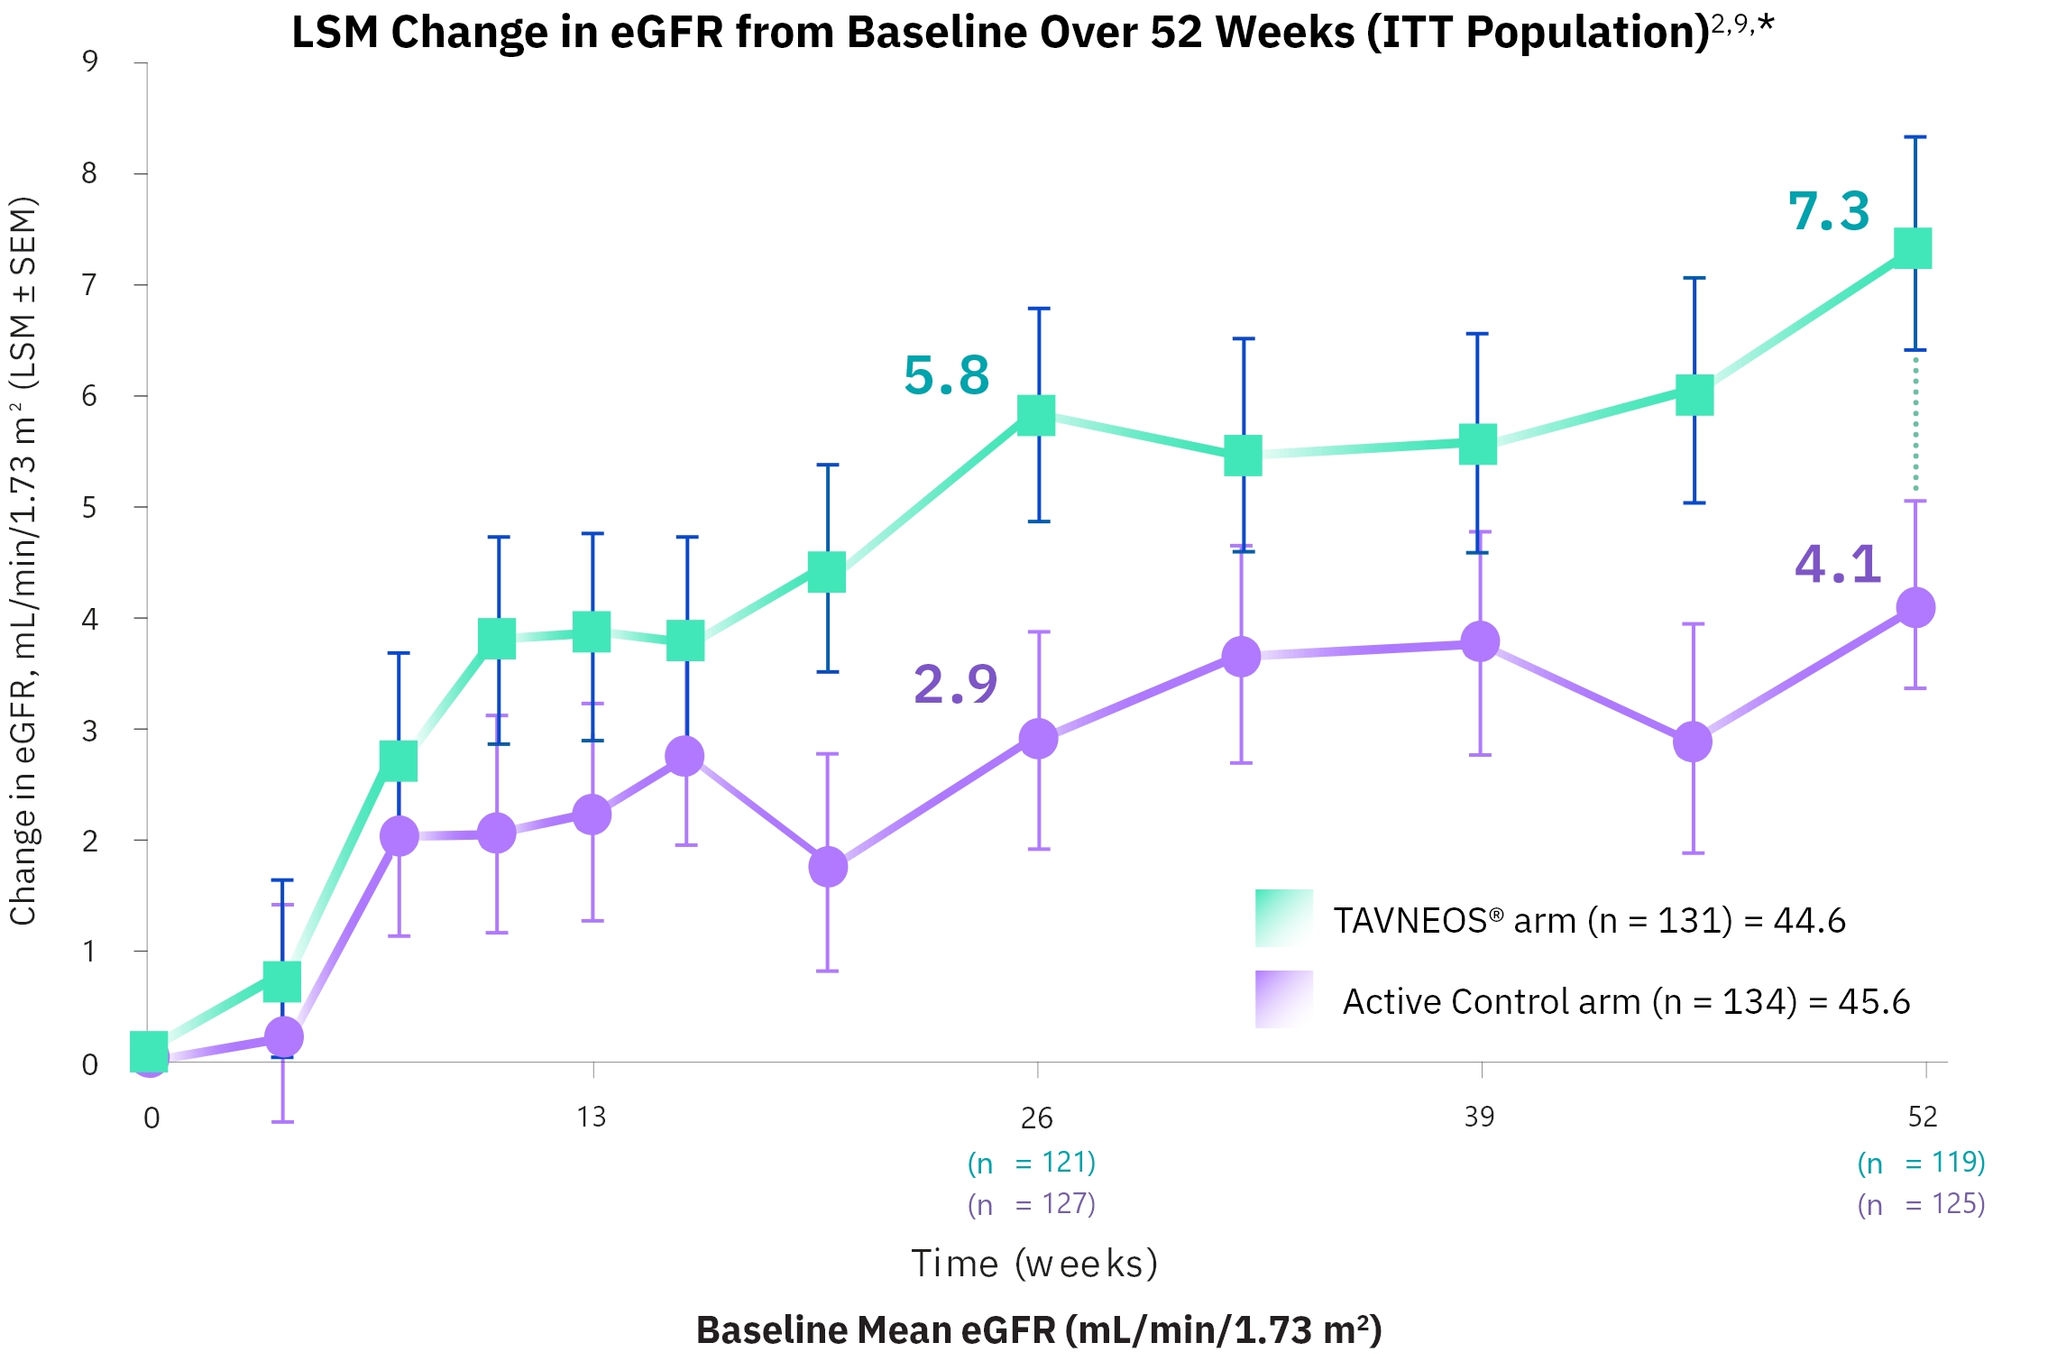
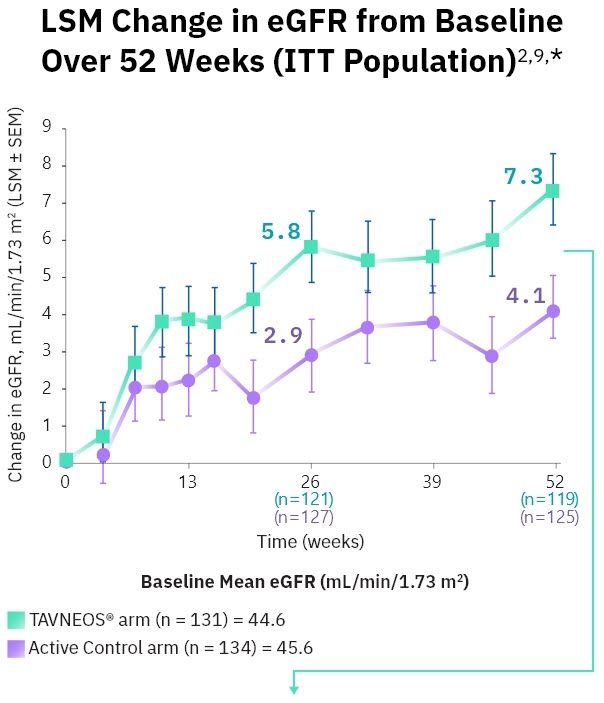
In patients with renal involvement at baseline, the TAVNEOS® arm saw an improvement in eGFR over 52 weeks2
3.2
mL/min/1.73 m2 LSM difference between the TAVNEOS® and Active Control arms (95% CI, 0.3-6.1)2
- 81.2% of patients in the trial had renal involvement based on the BVAS prior to treatment2
- Discontinuation of treatment with TAVNEOS® at Week 52 resulted in the reduction of treatment-induced difference in eGFR10
Prespecified secondary endpoint not adjusted for multiplicity and should be considered exploratory. Results should be interpreted with caution.2
*Least-squares mean (LSM) change in eGFR from baseline to Weeks 26 and 52 in patients with renal involvement at baseline based on the BVAS.
BVAS = Birmingham Vasculitis Activity Score; CI = confidence interval; eGFR = estimated glomerular filtration rate; ITT = intent to treat; SEM = standard error of the mean.
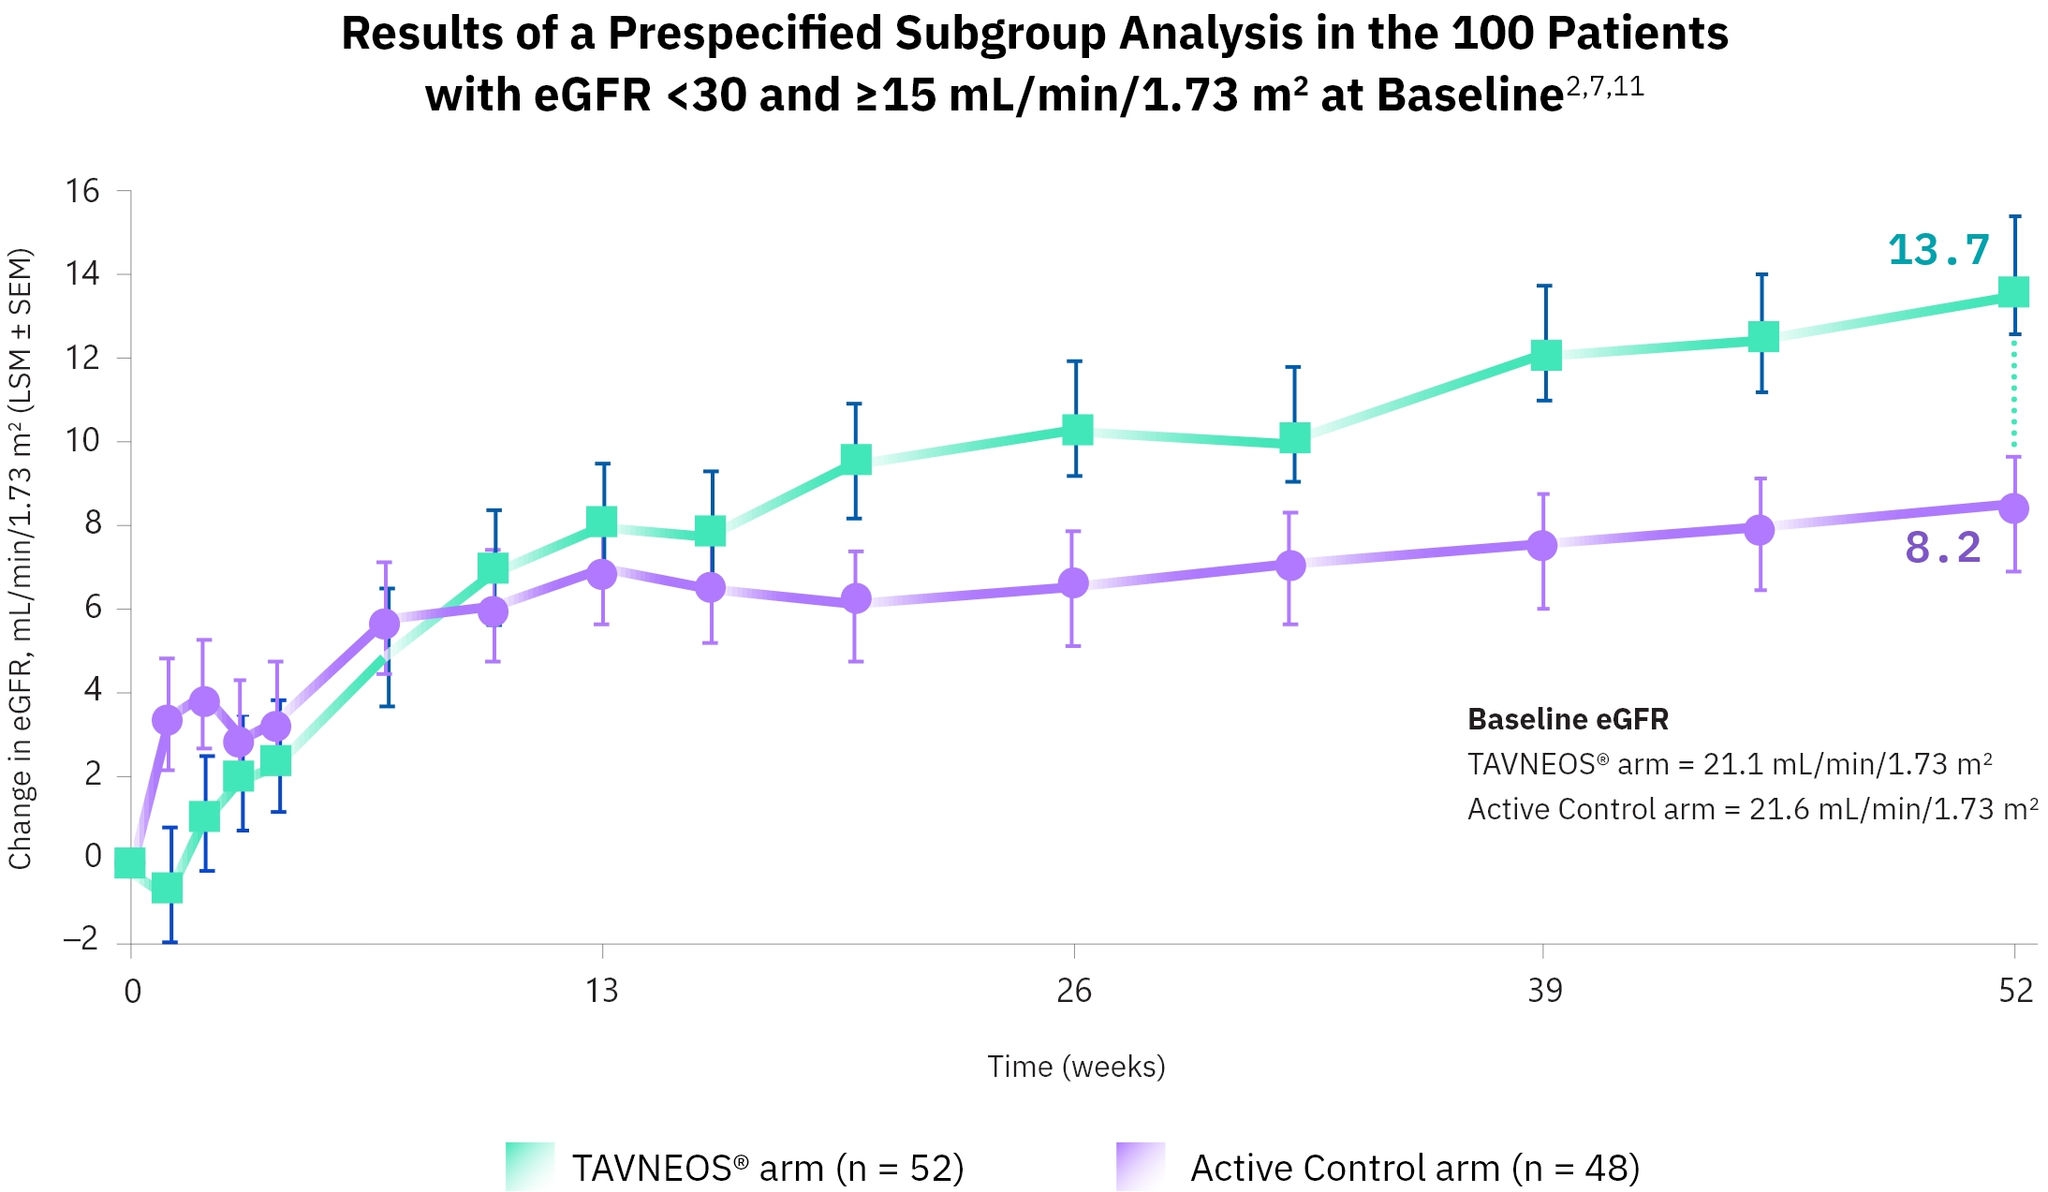
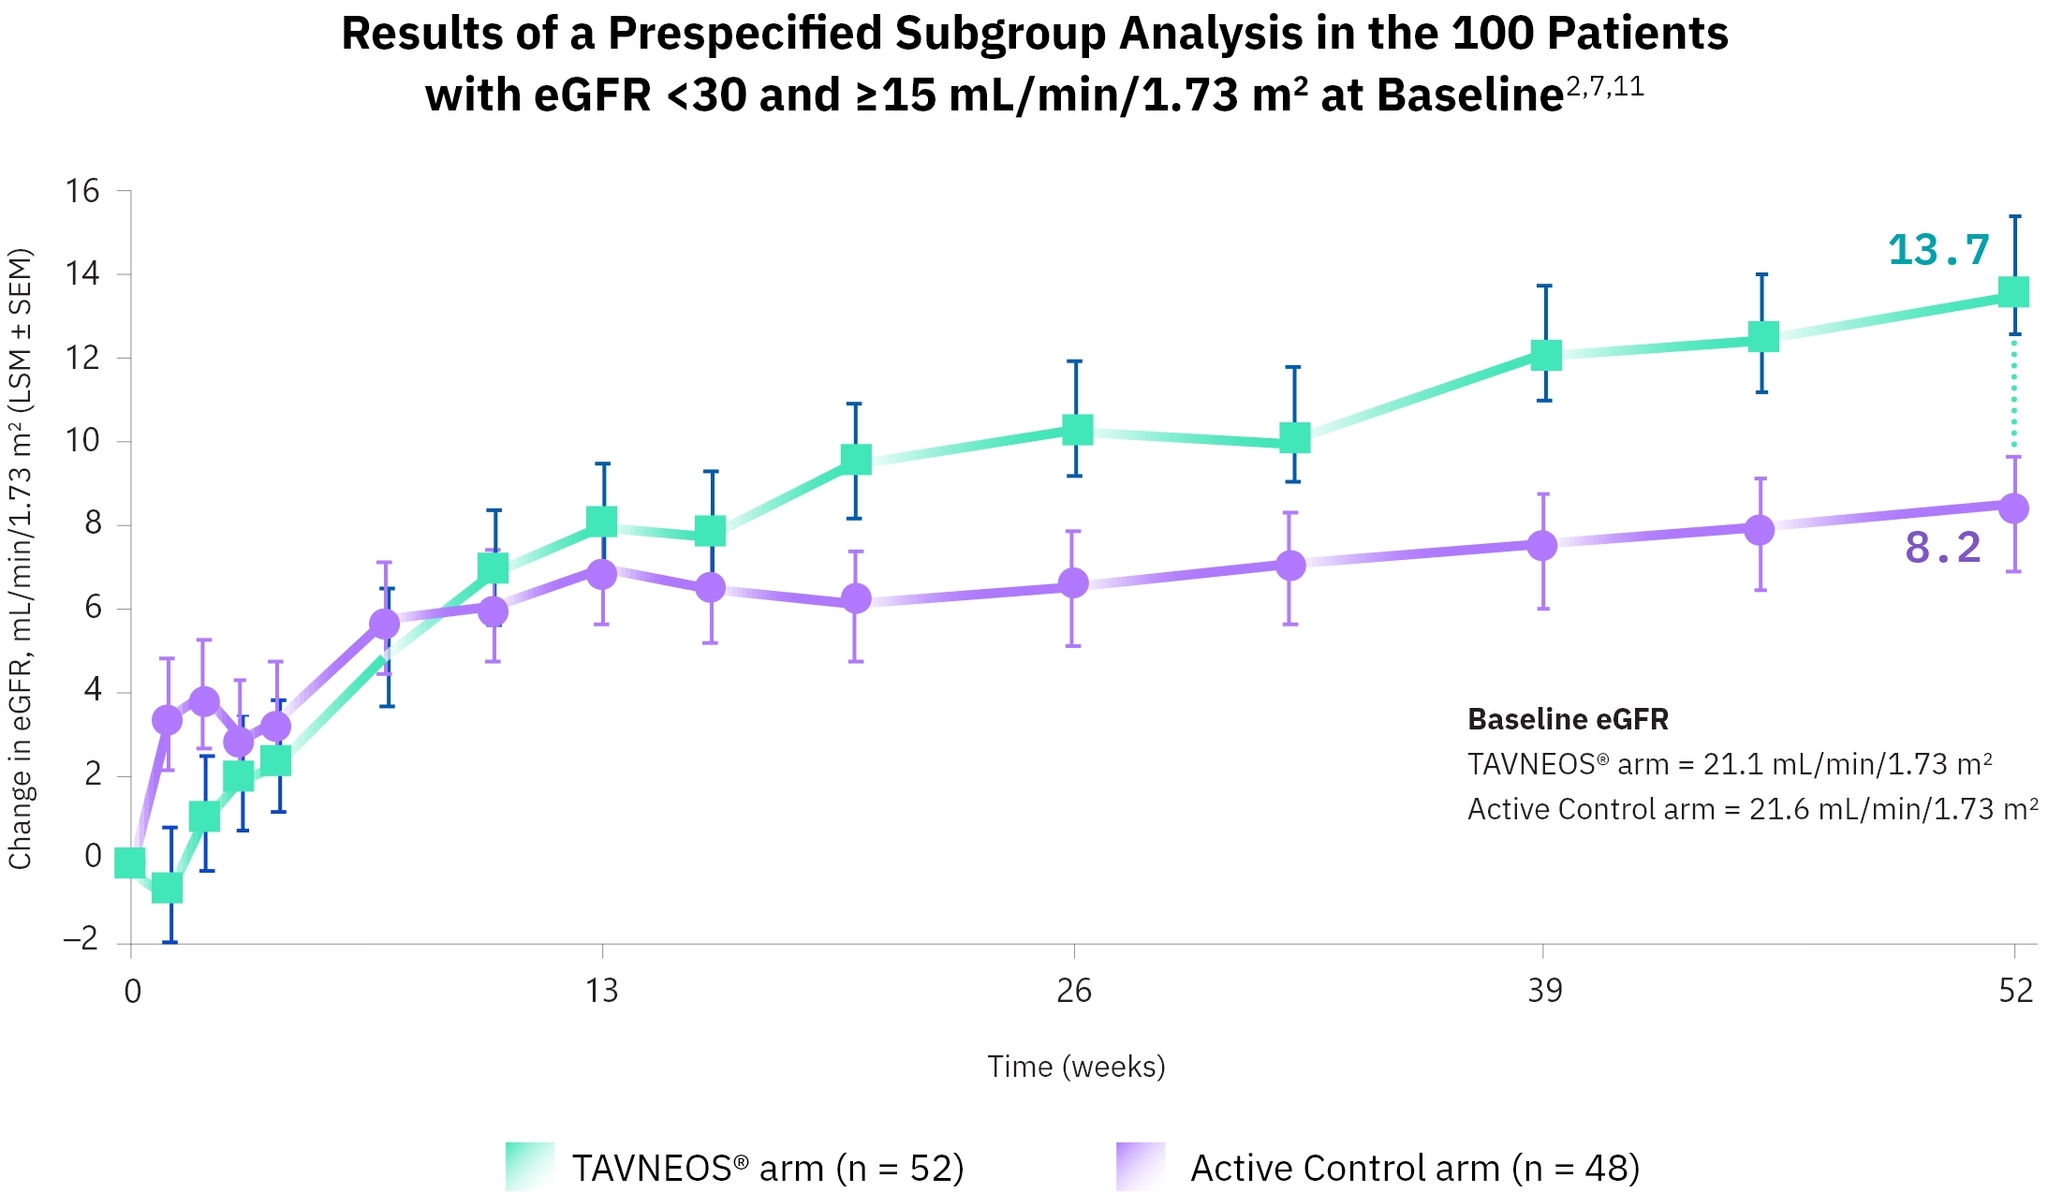
Subgroup analysis of patients with a baseline eGFR <30 and ≥15 (mL/min/1.73 m2)2,11
5.5
mL/min/1.73 m2 LSM difference between the TAVNEOS® arm and Active Control arm (95% CI, 1.7-9.5)2
Results from this exploratory subgroup analysis should be interpreted with caution.2
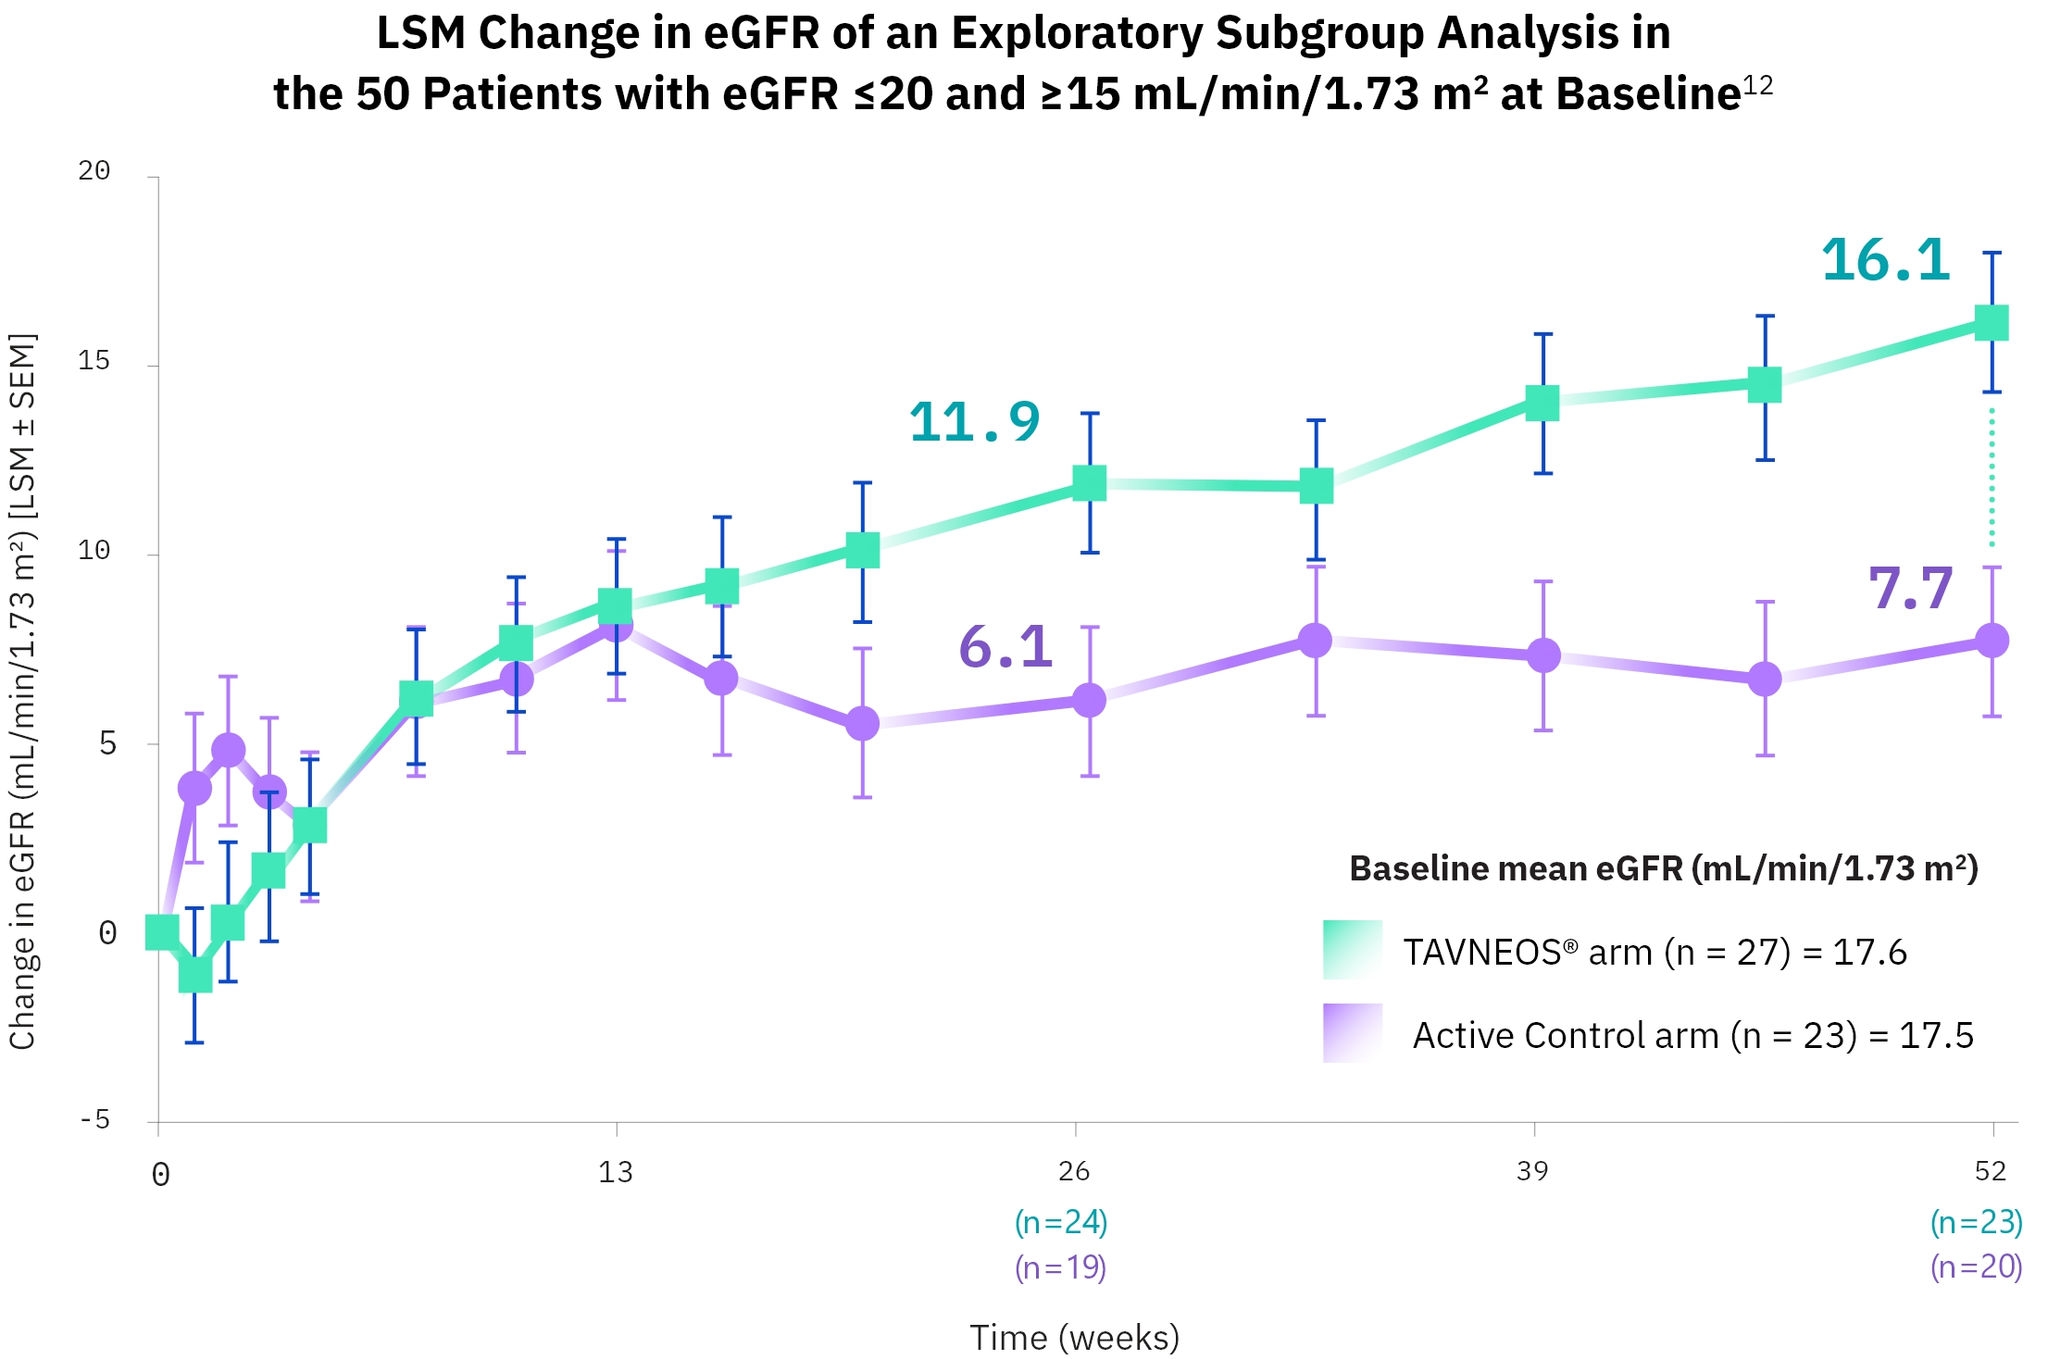
Post-hoc, exploratory subgroup analysis of patients with a baseline eGFR ≤20 and ≥15 (mL/min/1.73 m2)12
8.4
mL/min/1.73 m2 LSM difference between the TAVNEOS® and Active Control arms at Week 52 (95% CI, 2.9-13.8)12
Post-hoc analysis is exploratory and has not been adjusted for multiplicity. No conclusions of statistical or clinical significance can be drawn.12
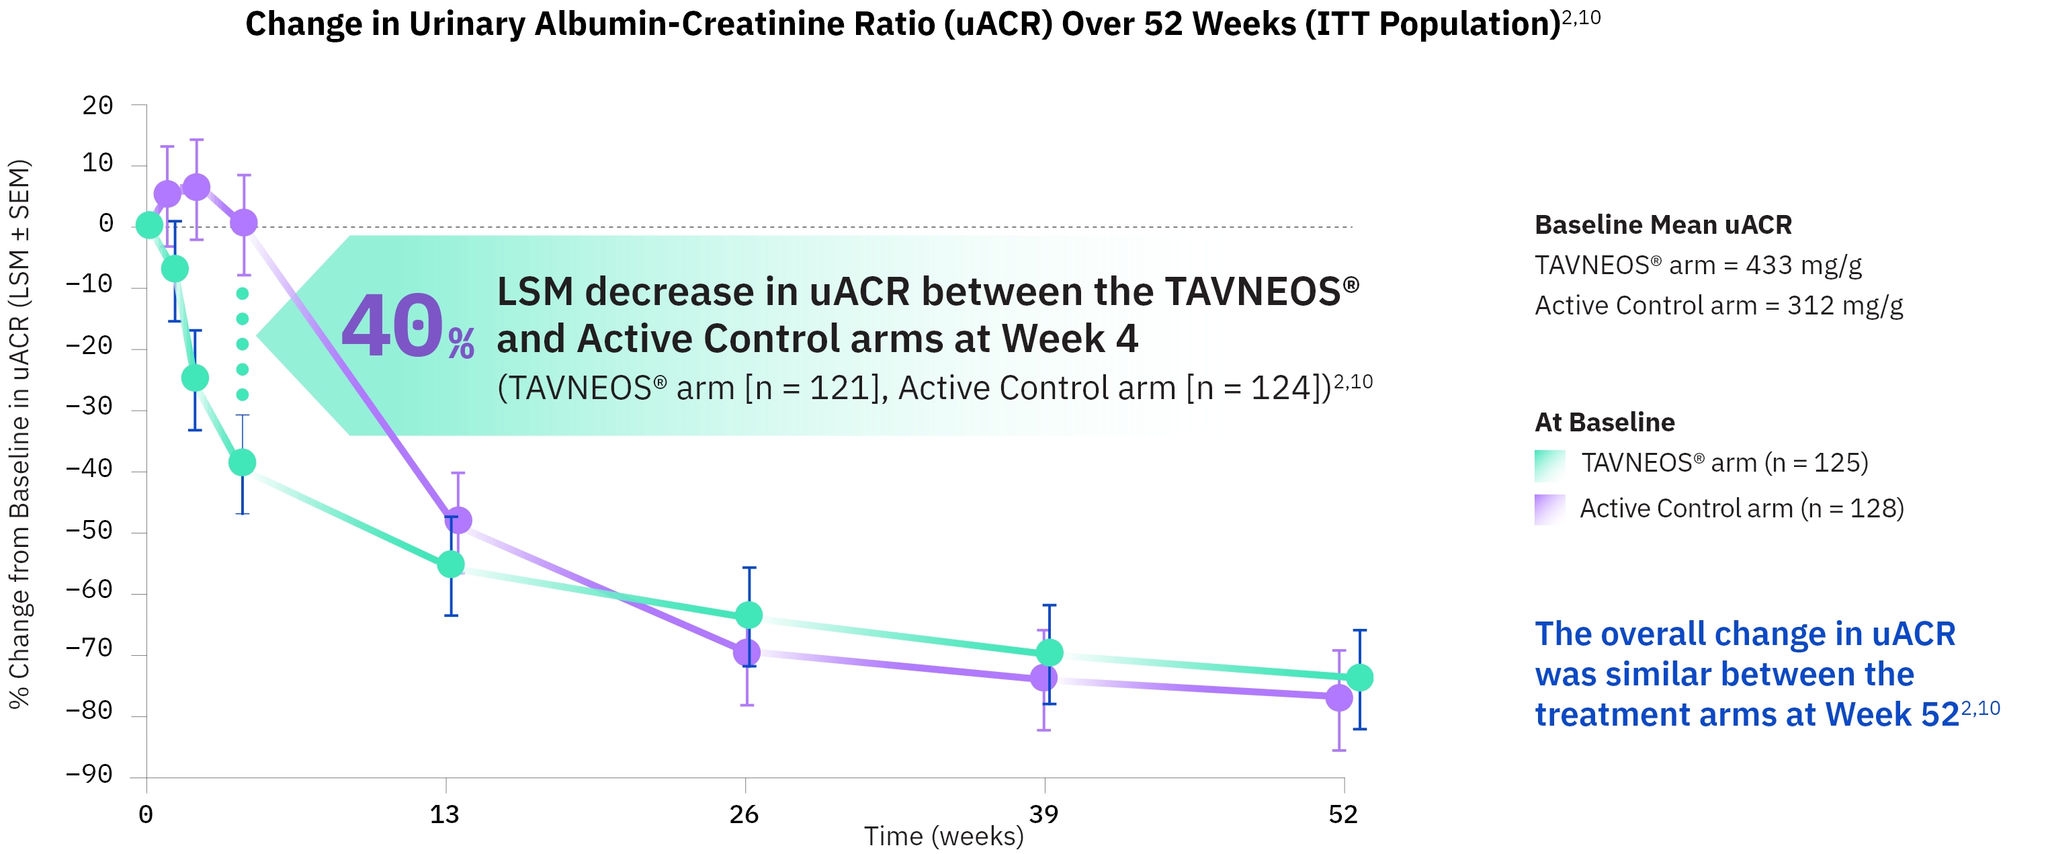
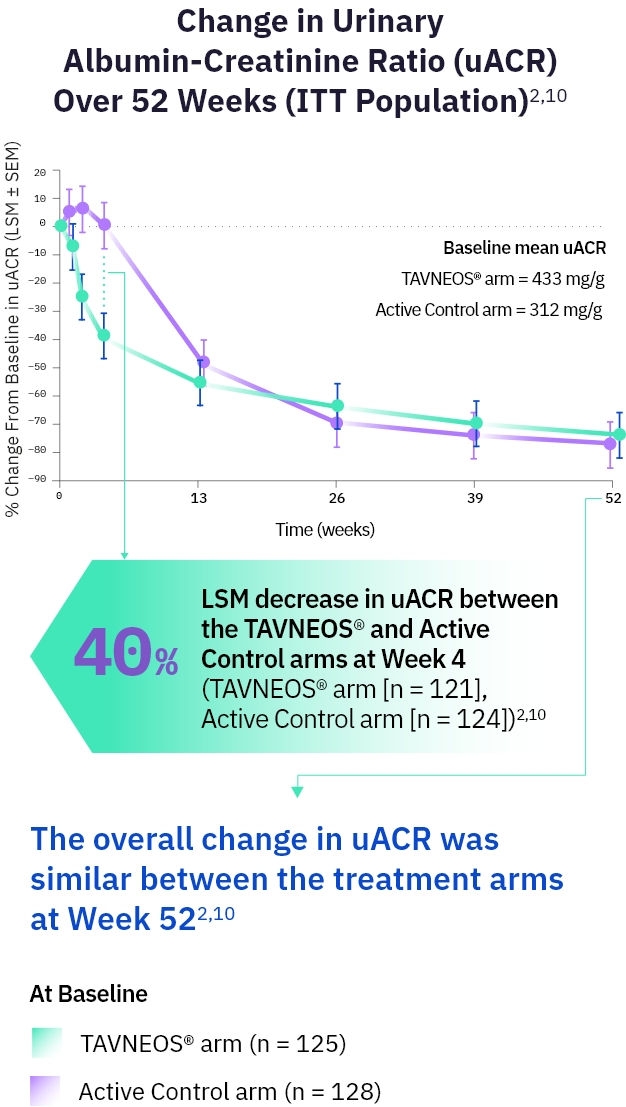
Patients in the TAVNEOS® arm saw a decrease in albuminuria by Week 42,10,†
Prespecified secondary endpoint of patients with renal involvement and albuminuria at baseline; analysis not adjusted for multiplicity and should be considered exploratory. Results should be interpreted with caution.2
- Elevated albuminuria may reflect underlying impairment of kidney function13,14
- Percent changes from baseline are based on ratios of geometric means of visit over baseline2
- The uACR analysis was only performed in patients who met BVAS criteria for renal involvement at baseline and who also had a uACR ≥10 mg albumin/g creatinine2
†Based on percentage change from baseline in uACR in patients with baseline renal involvement and baseline uACR ≥10 mg/g (52-week study period).2,10
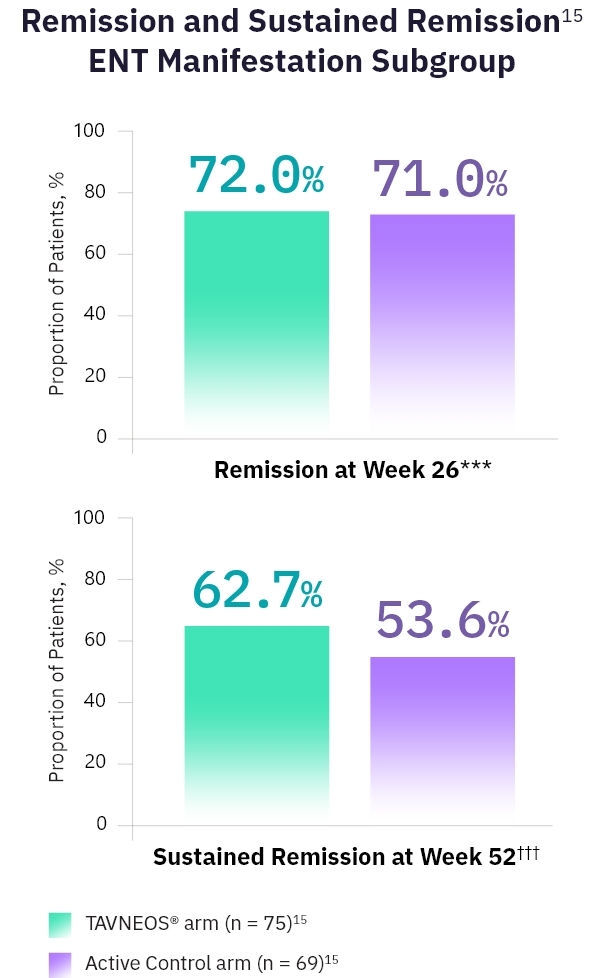
These post-hoc analyses of the ADVOCATE trial examined patients with baseline lung and ENT manifestations of vasculitis, according to the BVAS chest and ENT domains, in the TAVNEOS® arm and the Active Control arm15
Results from the 2019 ADVOCATE adjudication:
- The TAVNEOS® arm compared to the Active Control arm was non-inferior in achieving remission* at Week 26 and superior in sustaining remission† at Week 522
- Remission at Week 26: 72.3% (120/166) of patients in the TAVNEOS® arm vs 70.1% (115/164) in the Active Control arm (noninferiority, P < 0.001)2
- Sustained Remission at Week 52: 65.7% (109/166) of patients in the TAVNEOS® arm vs 54.9% (90/164) in the Active Control arm (superiority, P = 0.013)1,2
- Patients in the TAVNEOS® arm saw a 54% estimated reduction in risk of relapse2
- 10.1% of patients in the TAVNEOS® arm experienced a relapse compared to 21% of patients in the Active Control arm2
- Prespecified secondary endpoint not adjusted for multiplicity and subject to post-randomization variable dependence. Results should be interpreted with caution2
*Remission was defined as achieving a Birmingham Vasculitis Activity Score (BVAS) of 0 and not taking glucocorticoids for treatment of GPA or MPA within 4 weeks prior to Week 26.
†Sustained remission was defined as remission at Week 26 and at Week 52 (defined as a BVAS of 0 and no glucocorticoid use for treatment of GPA or MPA for 4 weeks before week 52), and without relapse‡ between Week 26 and Week 52.
‡Relapse was defined as the occurrence of 1 or 2 non-major items for at least 2 consecutive visits, at least 1 major item, or at least 3 non-major items based on the BVAS after a BVAS of 0 had been achieved.
Post-hoc analysis results from the 2019 ADVOCATE adjudication:
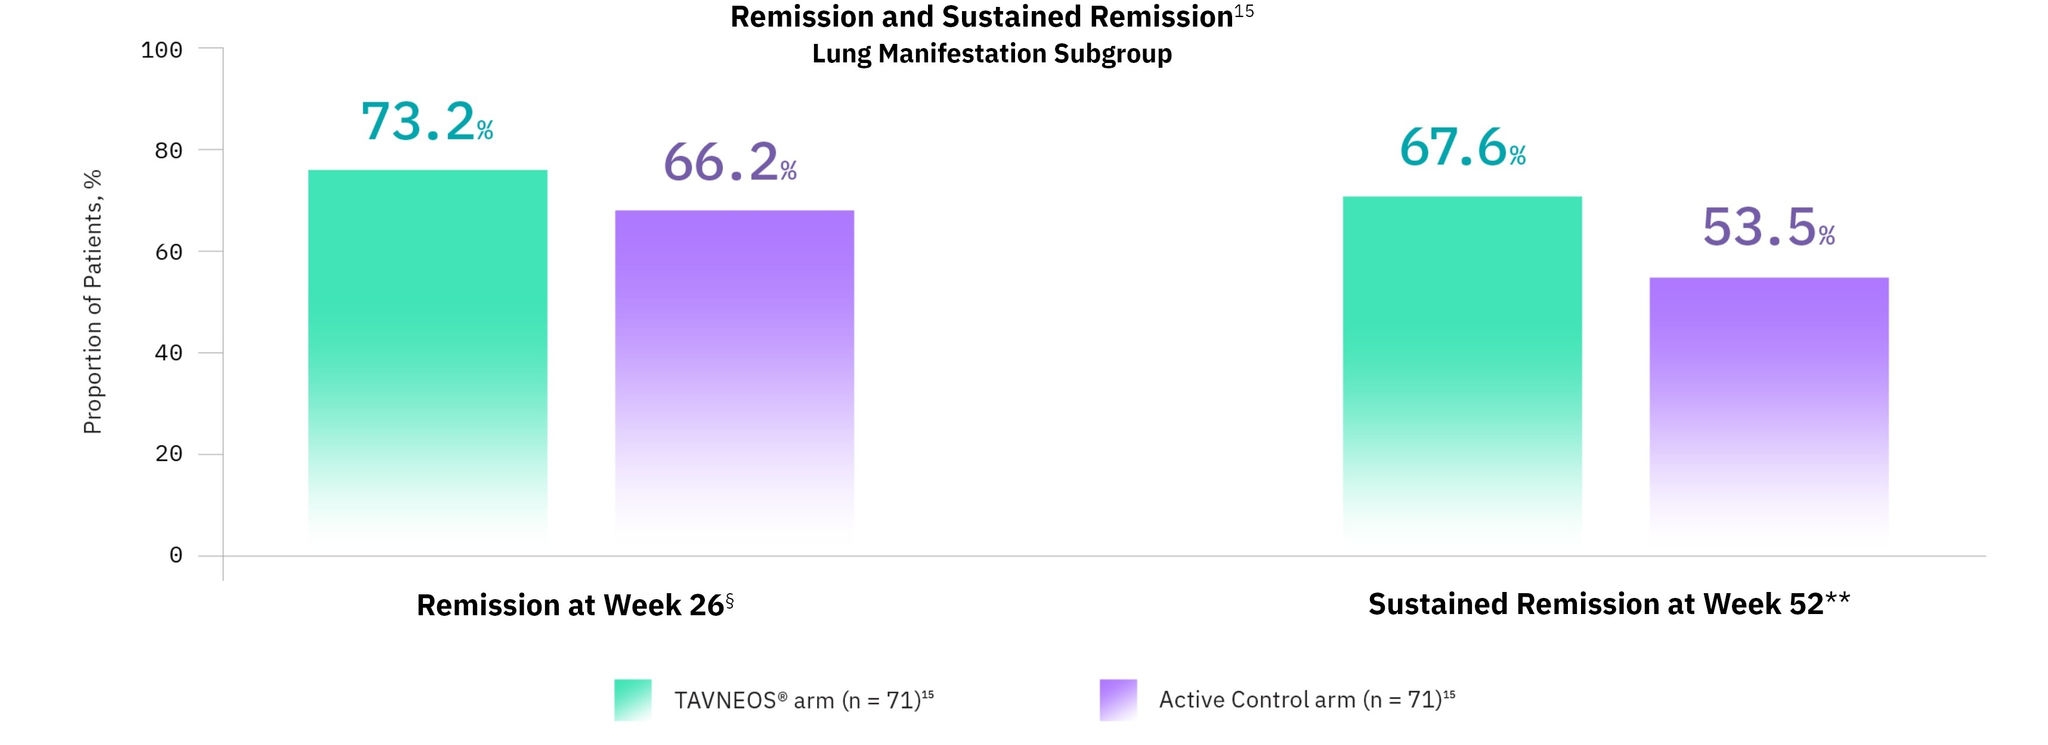
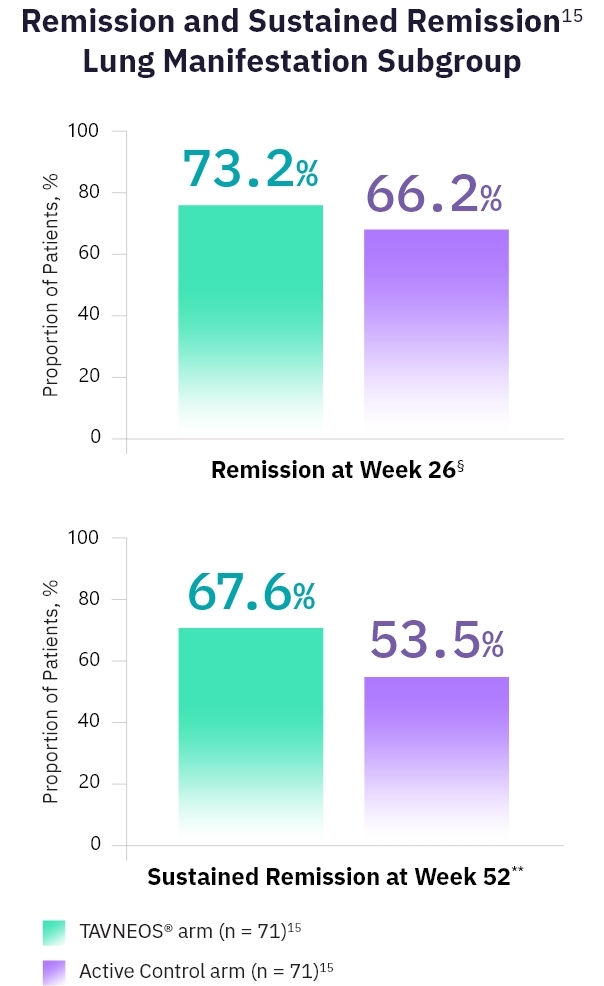
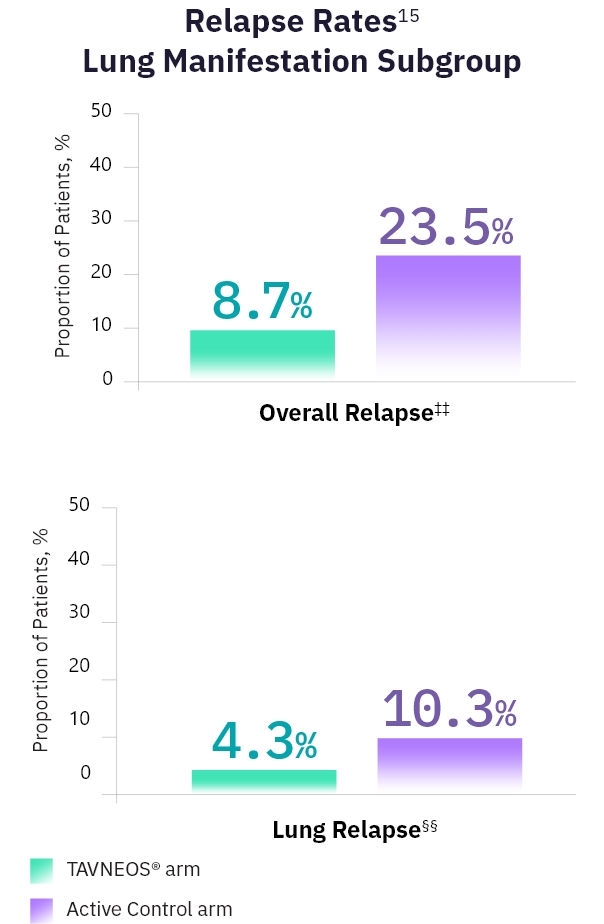
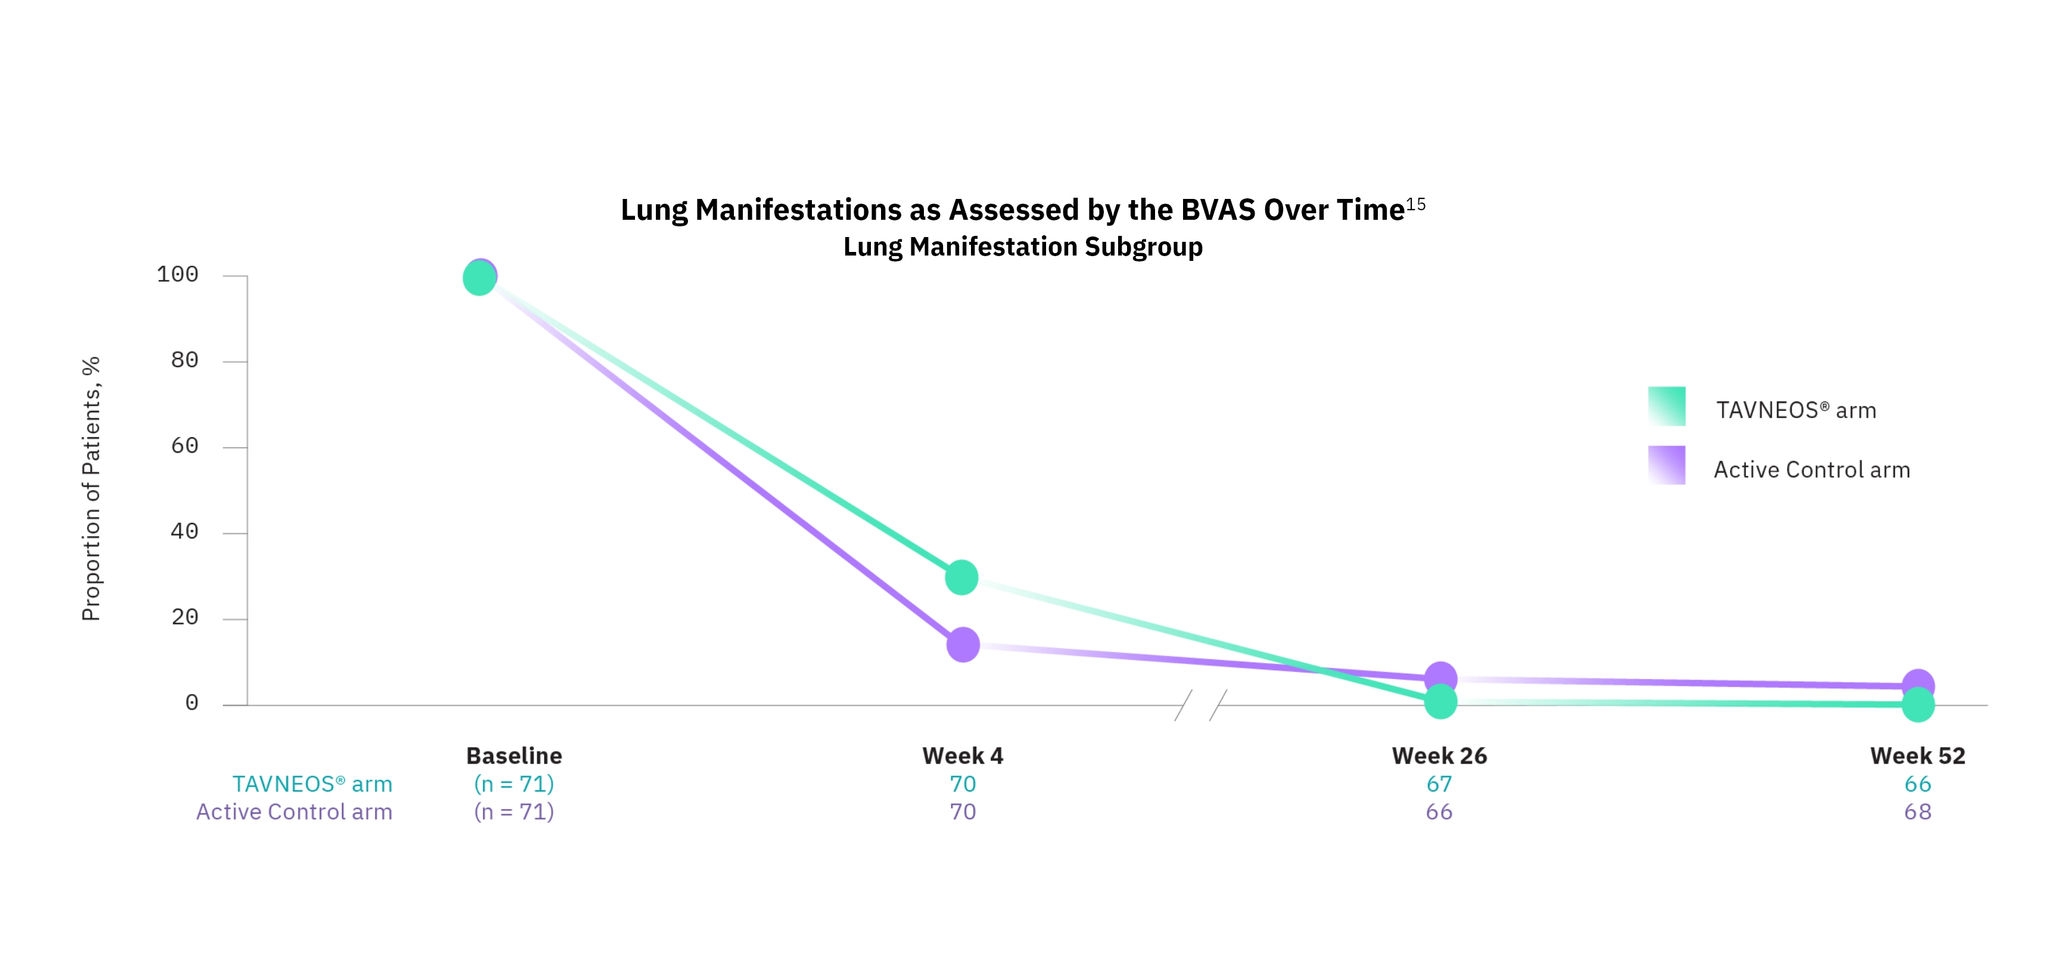
Lung Outcomes
These analyses were not prespecified. The lung manifestations evaluated included: wheeze, nodules or cavities, pleural effusion/pleurisy, infiltrate, endobronchial involvement, massive hemoptysis/alveolar hemorrhage, and respiratory failure.15,16
Post-hoc subgroup analysis is exploratory and has not been adjusted for multiple comparisons. No conclusions of statistical or clinical significance can be drawn.15
§Remission was defined as achieving a BVAS of 0 and not taking glucocorticoids for treatment of GPA or MPA for 4 weeks before Week 26.
**Sustained remission was defined as remission at Week 26 and at Week 52 (defined as achieving a BVAS of 0 and no use of glucocorticoids for treatment of GPA and MPA for 4 weeks before Week 52), and without relapse†† between Week 26 and Week 52.15
††Relapse was defined as the occurrence of 1 or 2 non-major items for at least 2 consecutive visits, at least 1 major item, or at least 3 non-major items based on the BVAS after a BVAS of 0 had been achieved.15
BVAS = Birmingham Vasculitis Activity Score.
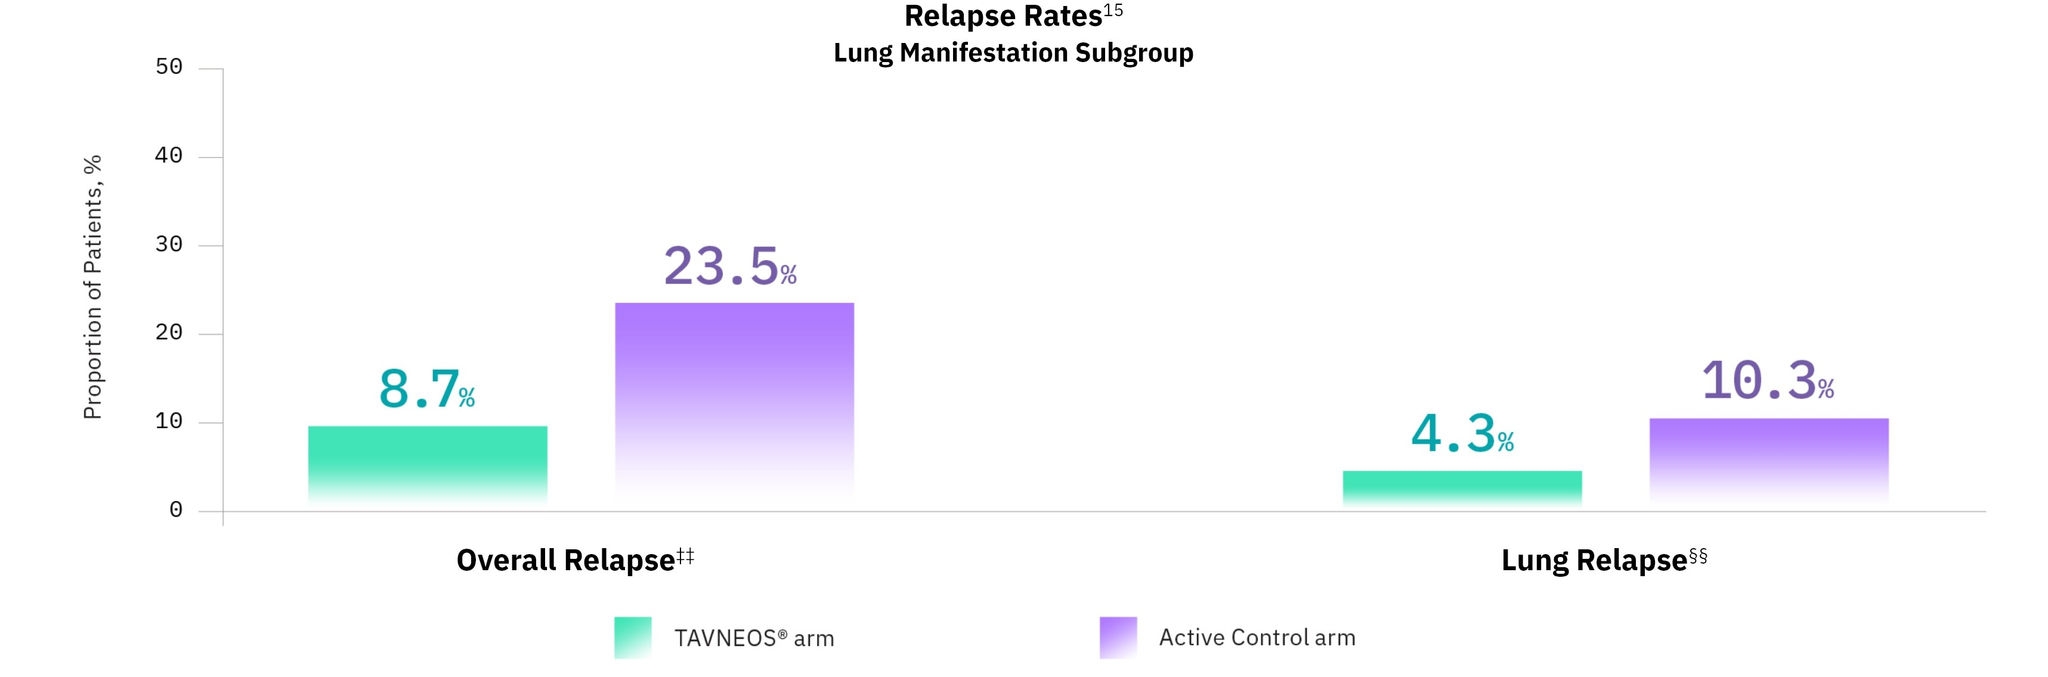
Post-hoc subgroup analysis is exploratory and has not been adjusted for multiple comparisons. No conclusions of statistical or clinical significance can be drawn.15
‡‡Relapse was defined as the occurrence of 1 or 2 minor items for at least 2 consecutive visits, at least 3 minor items, or at least 1 major item based on the BVAS after a BVAS of 0 had been achieved.15
§§Lung relapse was defined as a reoccurrence of any lung manifestation of vasculitis on the BVAS after a BVAS of 0 was first achieved for lung manifestations of vasculitis at any time during the 52-week treatment period.15
Post-hoc subgroup analysis is exploratory and has not been adjusted for multiple comparisons. No conclusions of statistical or clinical significance can be drawn.15
Baseline demographics and treatment characteristics were generally balanced between arms and across patients with lung manifestations.15
Post-hoc analysis results from the 2019 ADVOCATE adjudication:
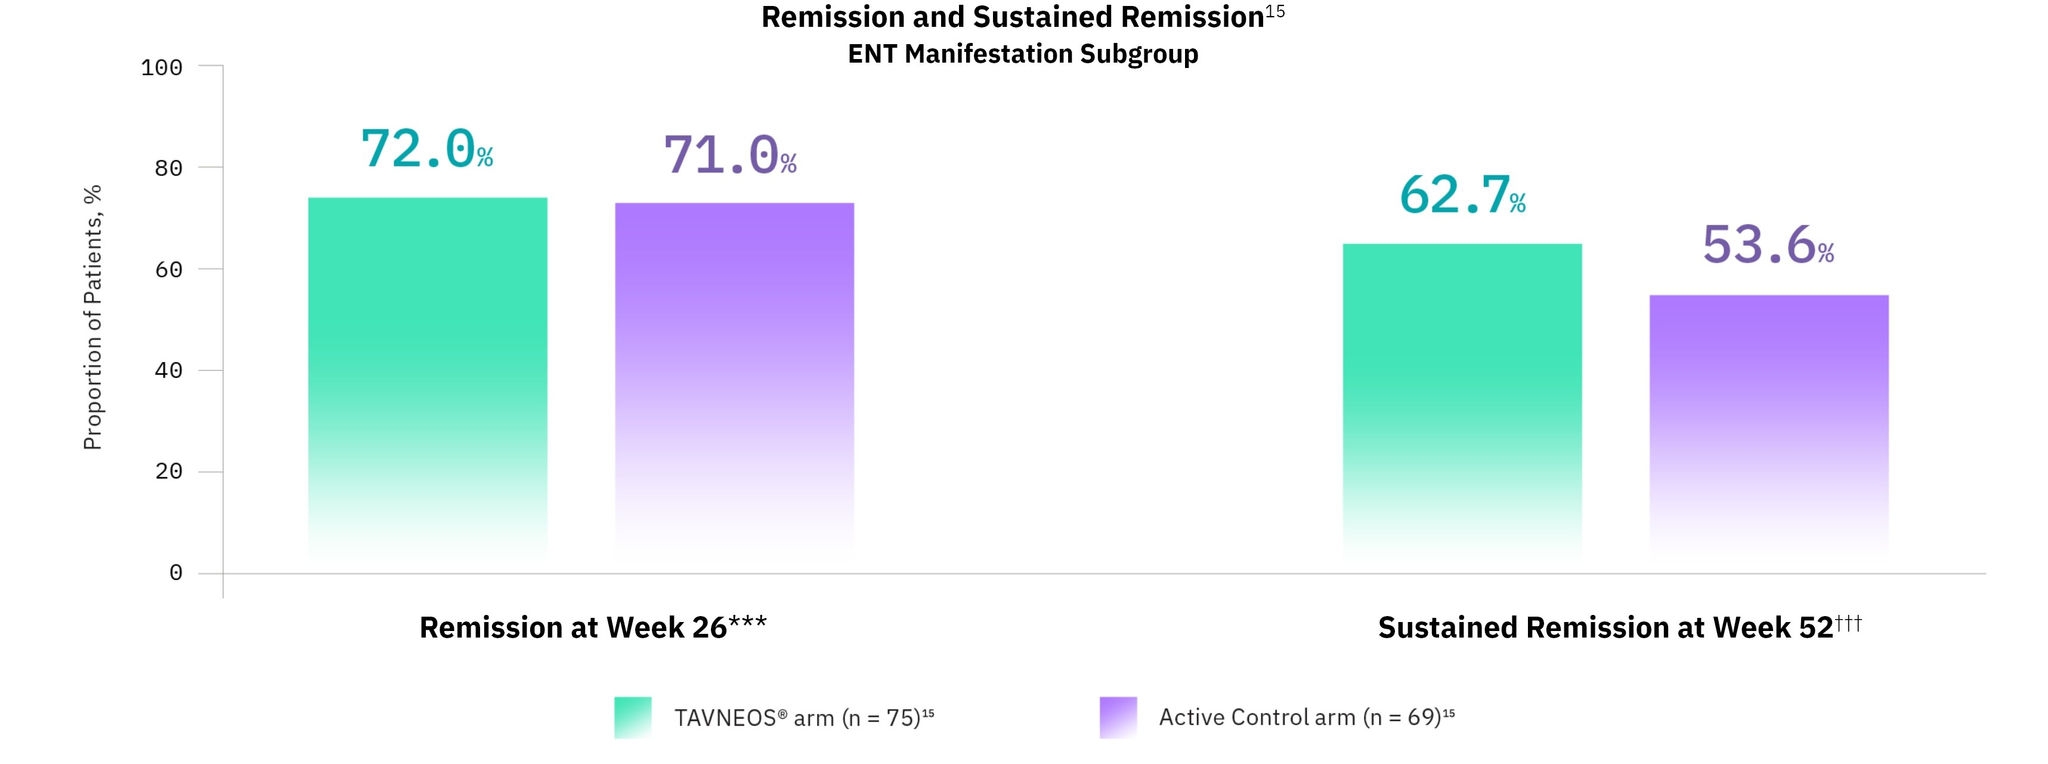
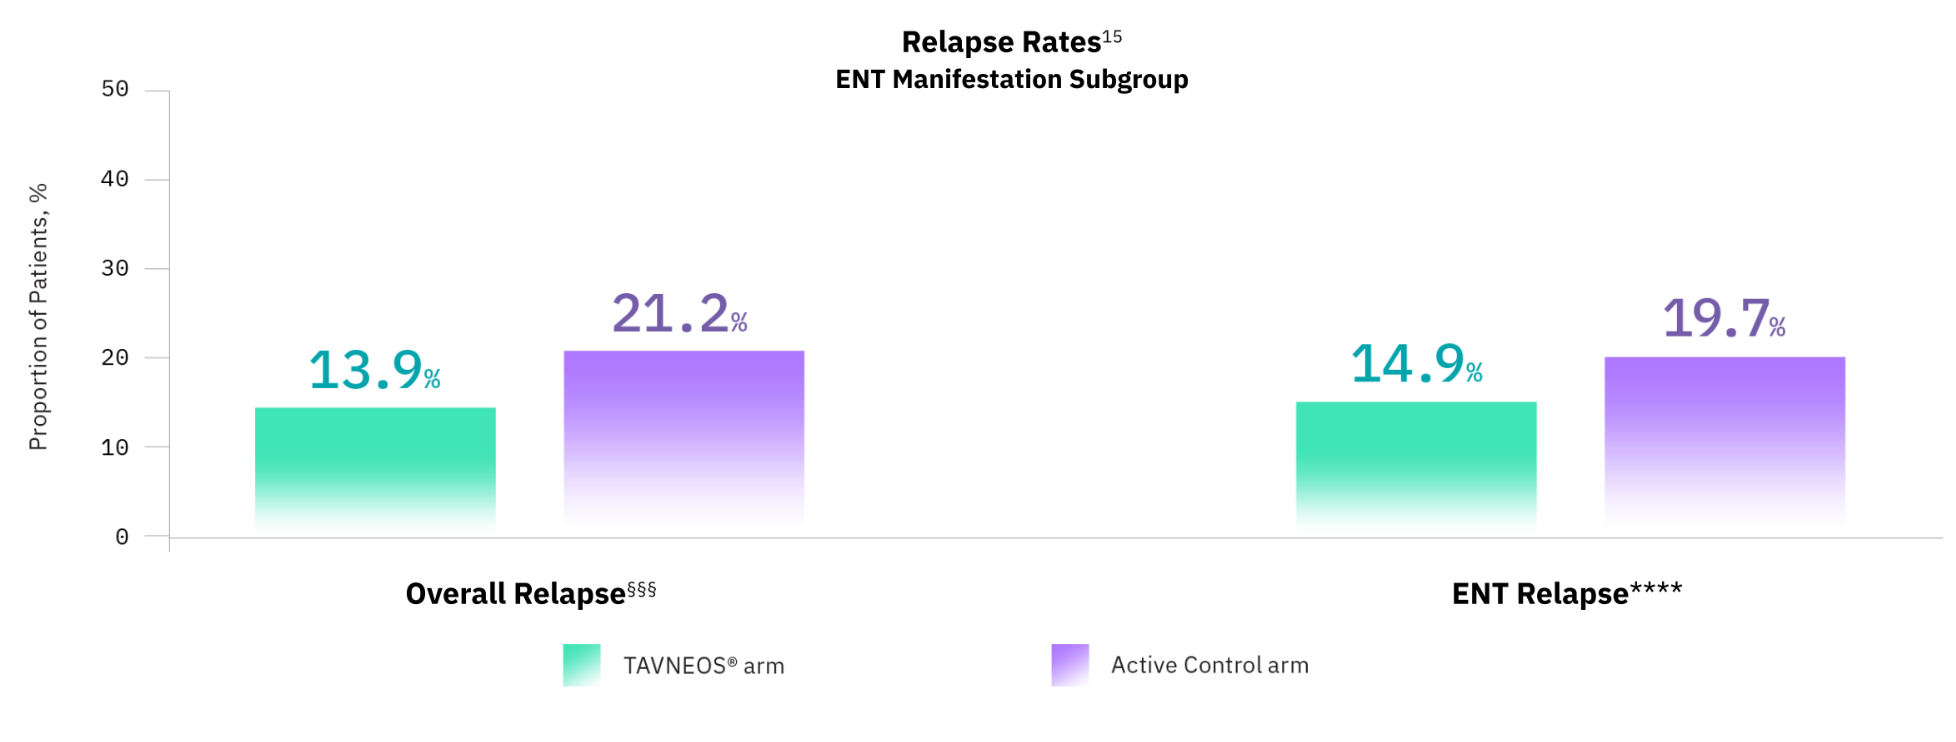
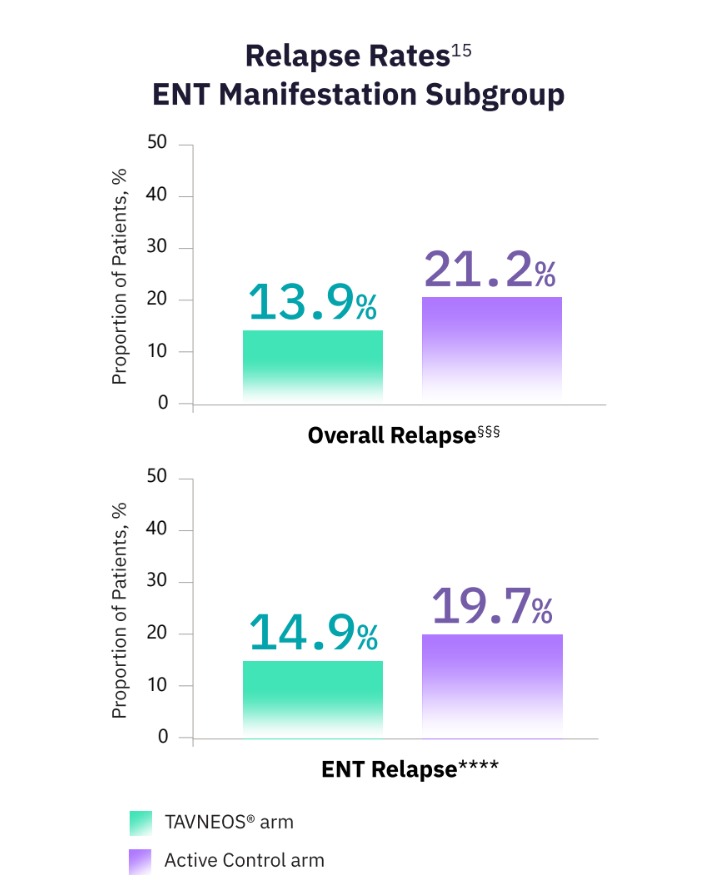
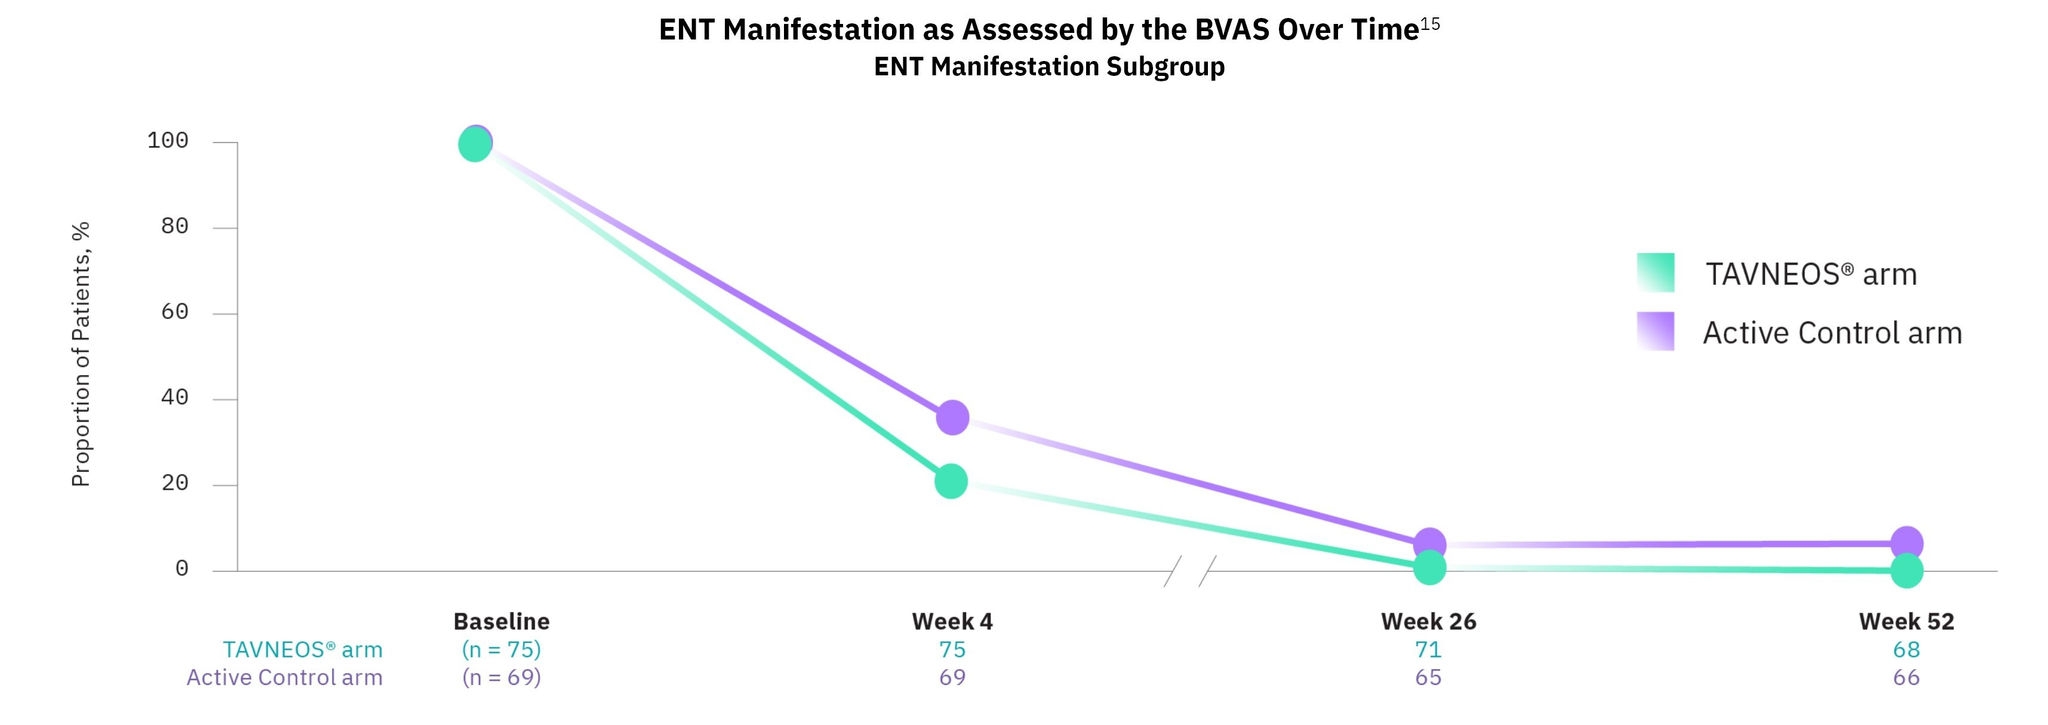
ENT Outcomes
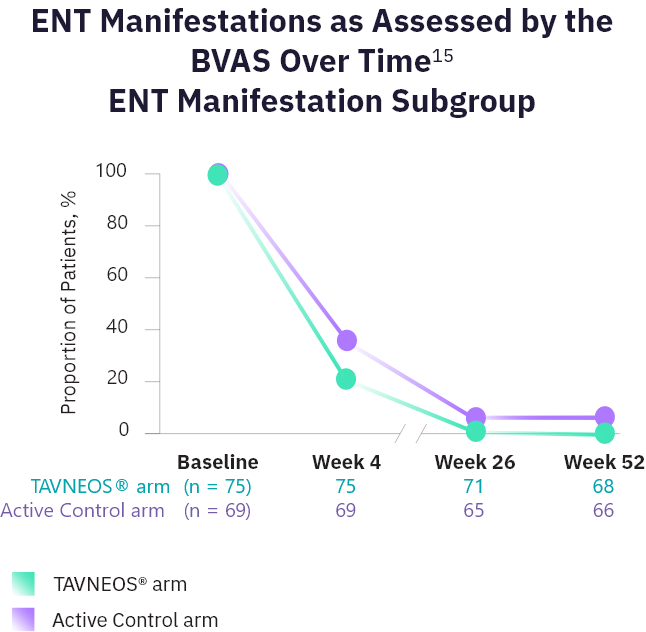
These analyses were not prespecified. The ENT manifestations evaluated included: bloody nasal discharge/crusts/ulcers/granulomata; paranasal sinus involvement; subglottic stenosis; conductive hearing loss; and sensorineural hearing loss.10,11
Post-hoc subgroup analysis is exploratory and has not been adjusted for multiple comparisons. No conclusions of statistical or clinical significance can be drawn.15
***Remission was defined as achieving a BVAS of 0 and not taking glucocorticoids for treatment of GPA or MPA for 4 weeks before Week 26.15
†††Sustained remission was defined as remission at Week 26 and at Week 52 (defined as achieving a BVAS of 0 and no use of glucocorticoids for treatment of GPA and MPA for 4 weeks before Week 52), and without relapse‡‡‡ between Week 26 and Week 52.15
‡‡‡Relapse was defined as the occurrence of 1 or 2 non-major items for at least 2 consecutive visits, at least 1 major item, or at least 3 non-major items based on the BVAS after a BVAS of 0 had been achieved.15
BVAS = Birmingham Vasculitis Activity Score; ENT = ear, nose, throat.
Post-hoc subgroup analysis is exploratory and has not been adjusted for multiple comparisons. No conclusions of statistical or clinical significance can be drawn.15
§§§Relapse was defined as the occurrence of 1 or 2 minor items for at least 2 consecutive visits, at least 3 minor items, or at least 1 major item based on the BVAS after a BVAS of 0 had been achieved.15
****ENT relapse was defined as a reoccurrence of any ENT manifestation of vasculitis on the BVAS after a BVAS of 0 was first achieved for ENT manifestations of vasculitis at any time during the 52-week treatment period.15
Post-hoc subgroup analysis is exploratory and has not been adjusted for multiple comparisons. No conclusions of statistical or clinical significance can be drawn.15
Baseline demographics and treatment characteristics were generally balanced between arms and across patients with ENT manifestations.15
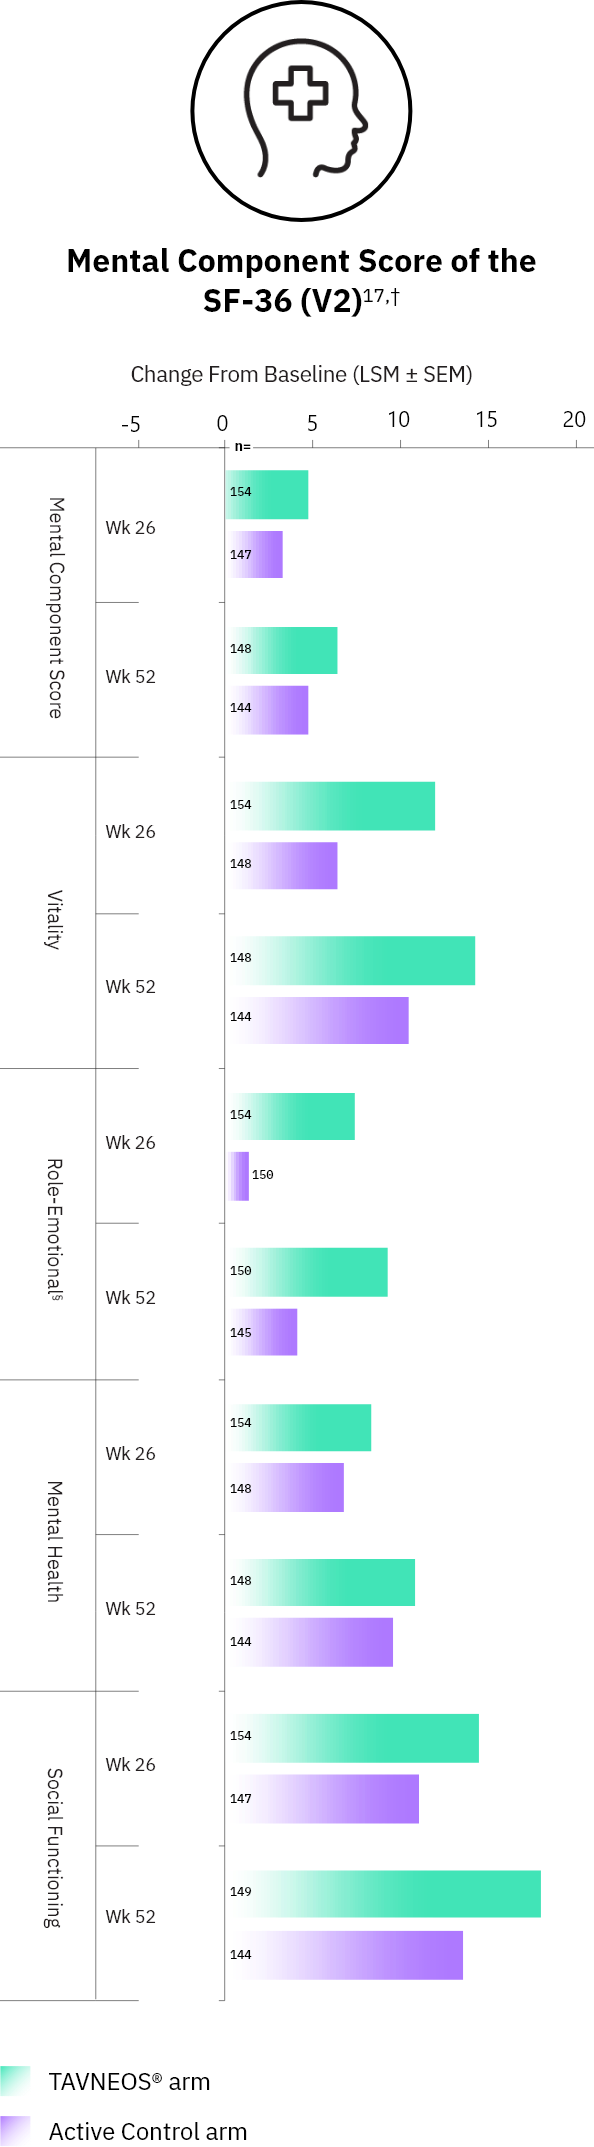
Patients in the TAVNEOS® arm experienced improved quality of life
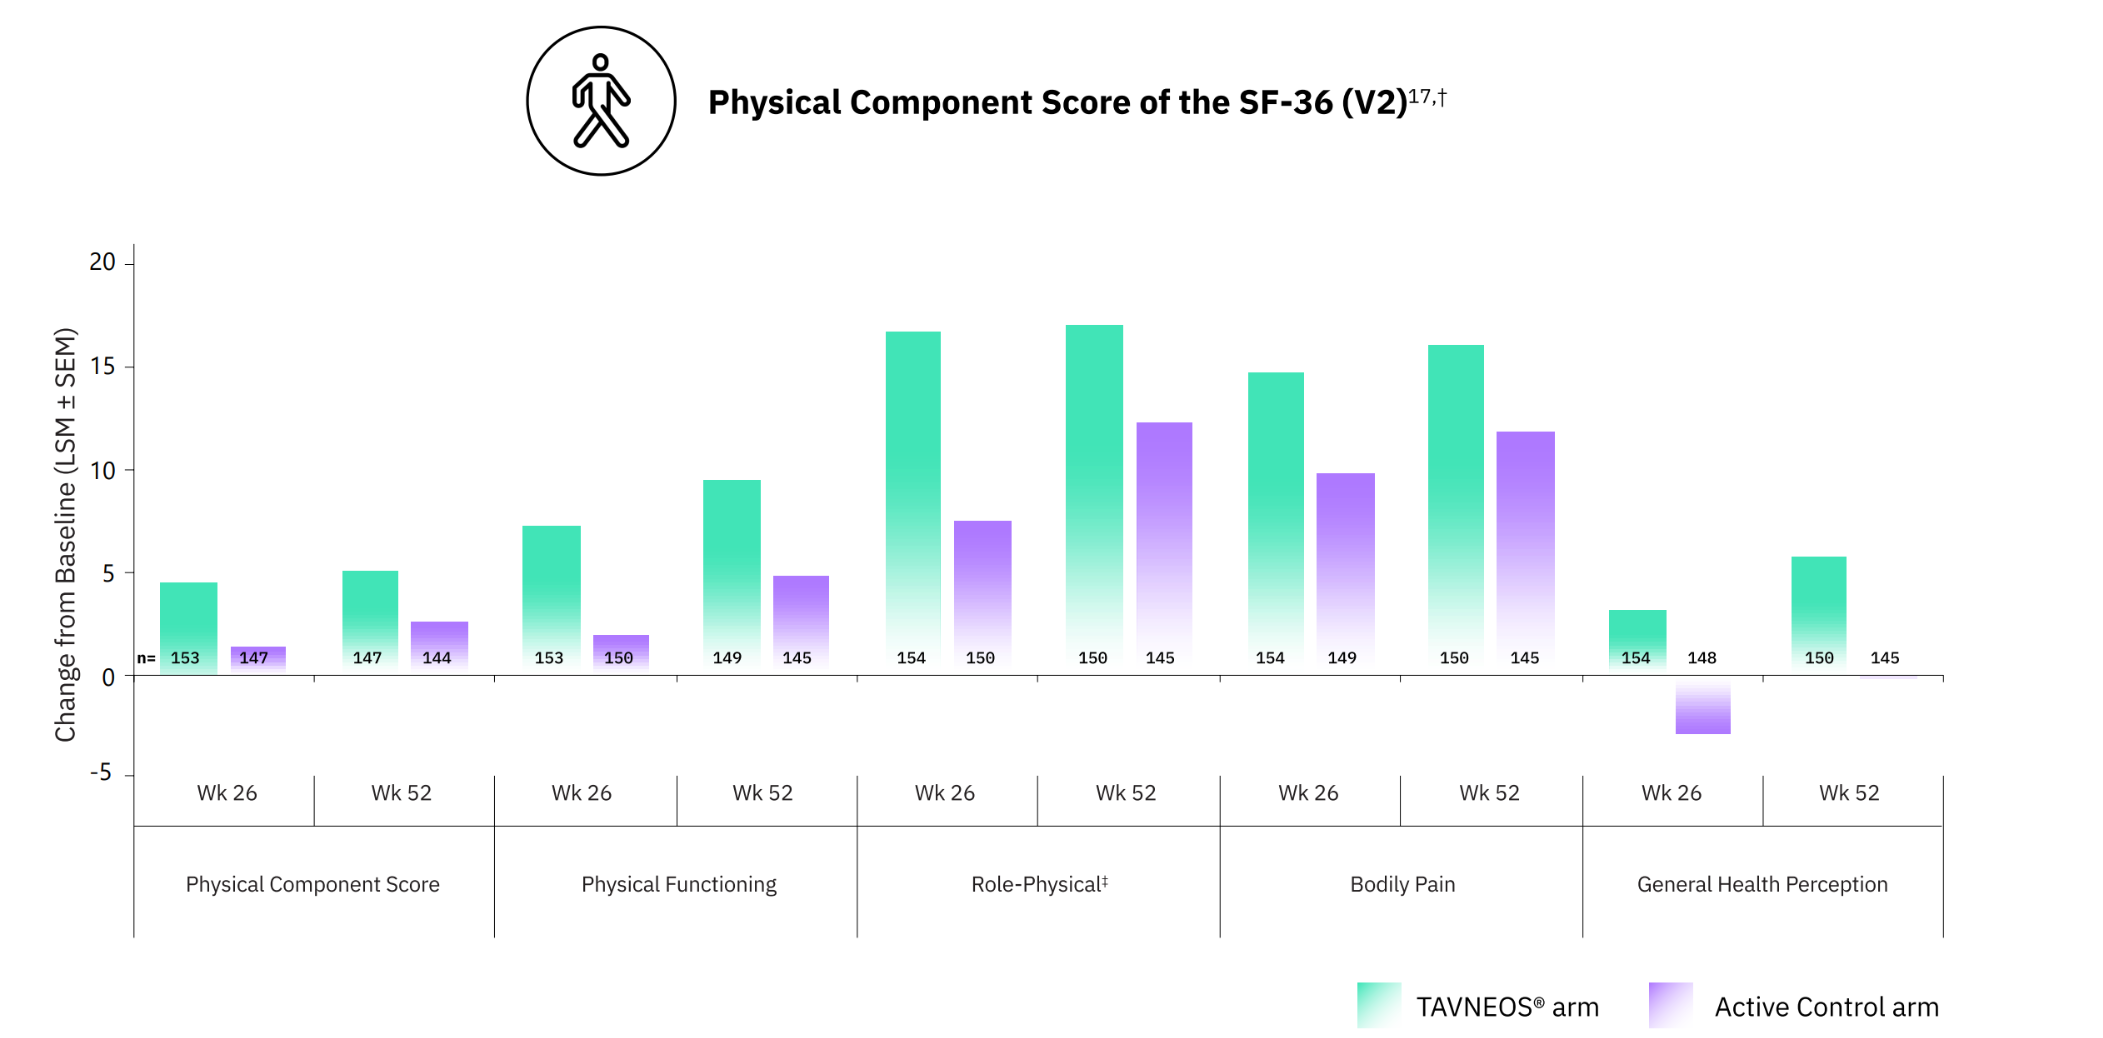
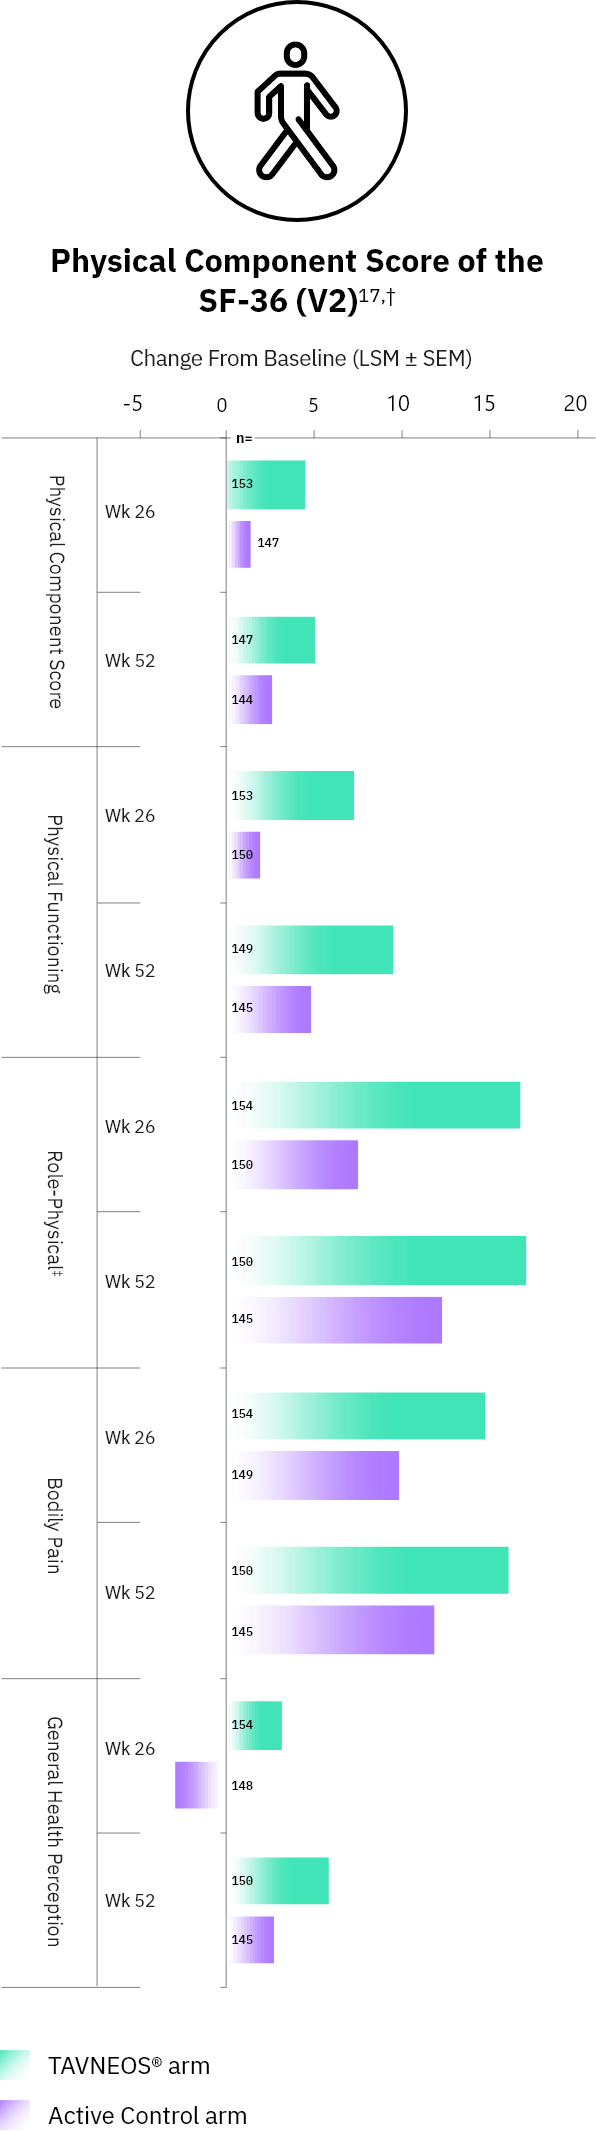
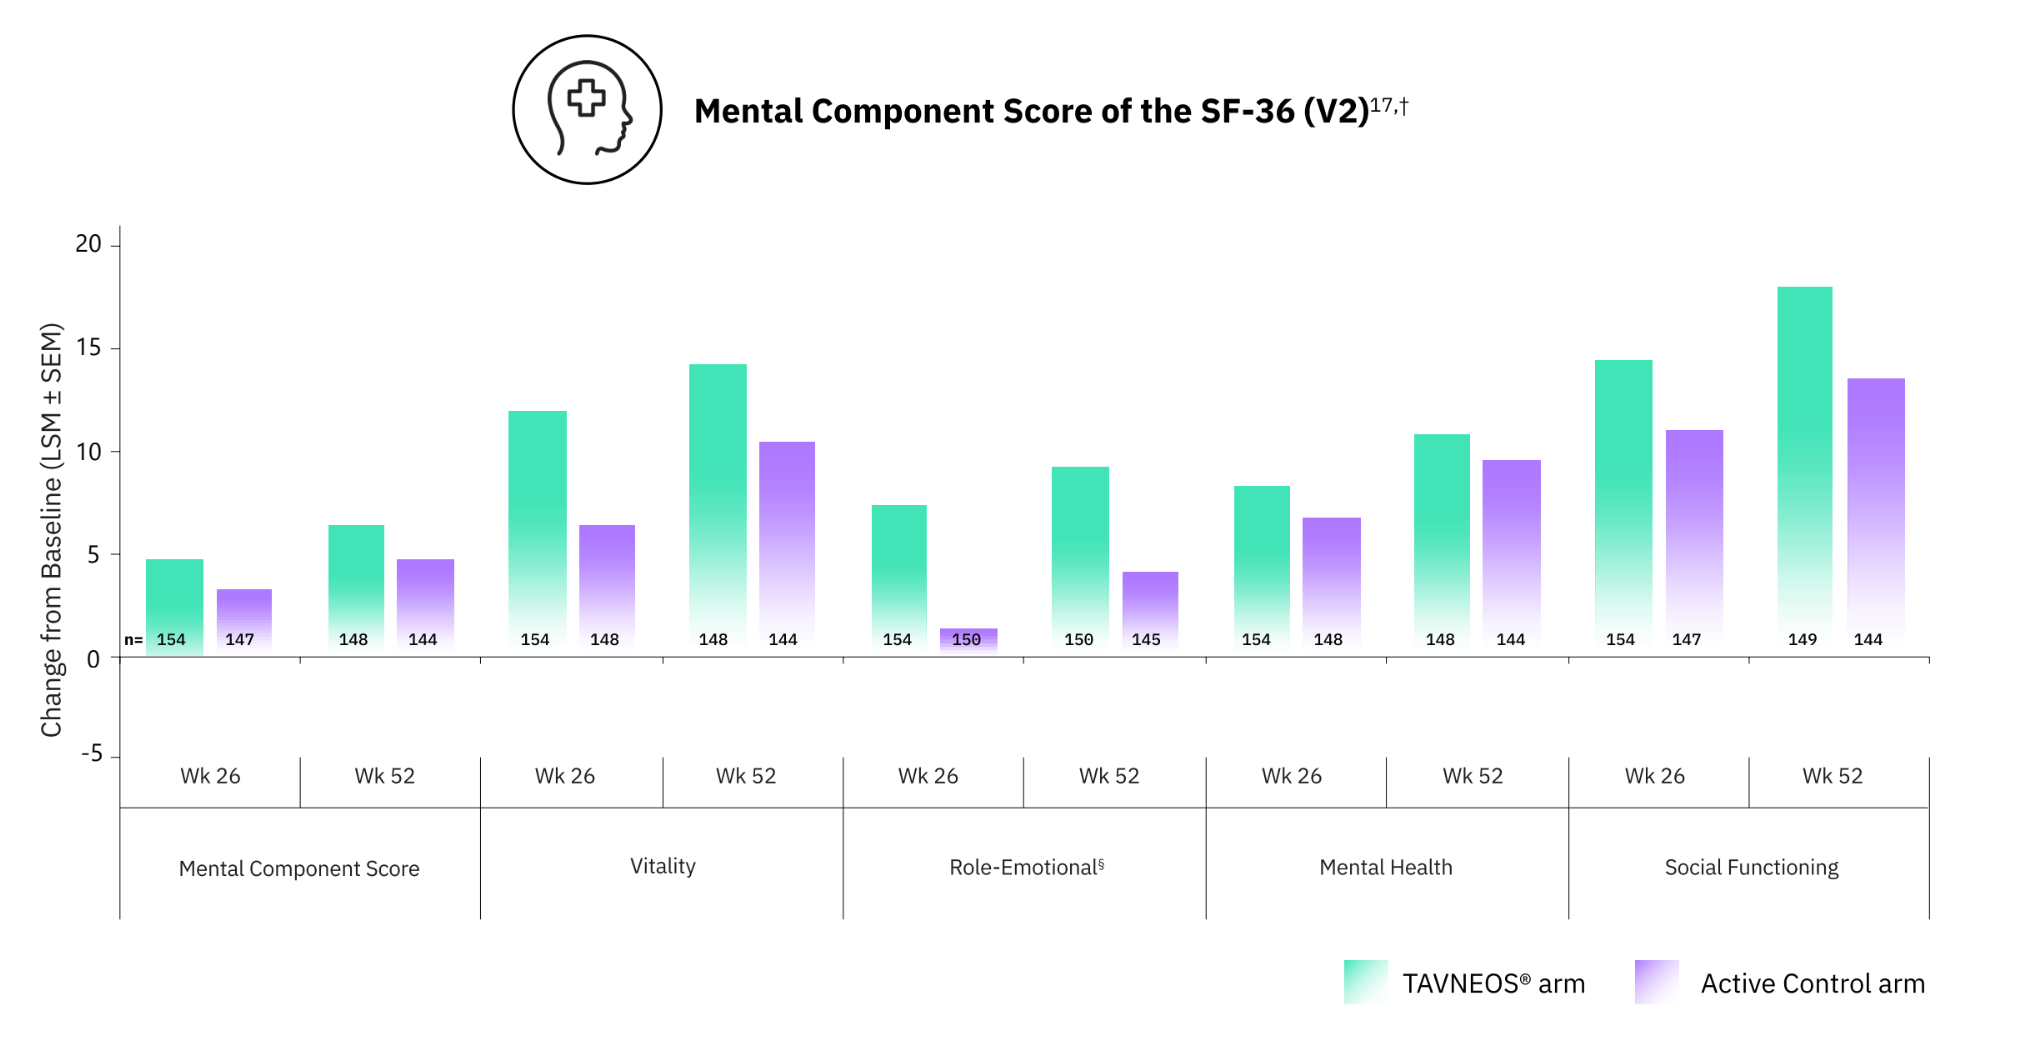
Patients in the TAVNEOS® arm reported greater improvement across physical and mental health-related quality-of-life metrics at Weeks 26 and 52 compared to patients in the Active Control arm10,*
Prespecified secondary endpoint not adjusted for multiplicity and should be considered exploratory. Results should be interpreted with caution. The SF-36 was not specifically validated for GPA and MPA.2
*As assessed by the 36-Item Short Form Health Survey (SF-36), version 2. SF-36 scores range from 0 (worst) to 100 (best).2
†Scores reflect change from baseline (least squares mean ± standard error of the mean).10
‡Role-Physical is one of the eight SF-36 domains. It assesses the limitations in routine activities because of physical health capabilities.18
§Role-Emotional is one of the eight SF-36 domains. It assesses the limitations on routine activities because of emotional factors.18